The Seed Oil Myths

The Truth About Seed Oils 

Author: Dr. Stephen Chaney 

The Seed Oil Myths

Myth Versus FactsYou’ve seen the claims. “You should avoid all seed oils. They are toxic.”

Any time you see claims like, “Avoid all…[add the food villain of the day]” or “[a certain food] is toxic” your “truth-meter” should go on high alert. Claims like that are more likely to be hype than truth.

More specifically, the claims about seed oils are:

  • They are heavily processed.
  • They contain toxic ingredients.
  • They are genetically modified.
  • They cause inflammation and oxidative damage.
  • They increase your risk of inflammatory diseases, heart disease, and cancer.
  • A healthier option is to replace seeds oils with animal foods high in saturated fats.

Like any good food myth, there is a kernel of truth to each of these claims. In this article I will describe the kernel of truth associated with each of these claims, put them into perspective, and give practical guidelines for incorporating seed oils into your diet.

The topics I will cover are:

  • The truth about fats.
  • The truth about omega-6 fats.
  • The truth about saturated fats.
  • The truth about canola oil.
  • The truth about seed oils.

The Truth About Fats

The health authorities and media must think the American public is stupid. They oversimplify everything. They tell us:

  • Animal fats are saturated fat.
  • Olive oil is monounsaturated fat.
  • Vegetable oils are omega-6 polyunsaturated fat.
  • Fish oil is omega-3 polyunsaturated fat.

The truth is that every naturally occurring fat and oil is a mixture of all four kinds of fat. And each food contains a unique mixture of fats. The kernel of truth is:

  • Animal fats have a higher percentage of saturated fat than other fats and oils.
  • Olive oil has a higher percentage of monounsaturated fat than other oils.
  • Vegetable oils have a higher percentage of omega-6 polyunsaturated fat than other oils.
  • Fish oil has a higher percentage of omega-3 polyunsaturated fat than other oils.


But the full truth is that each food contains a unique mixture of fats. For example,

  • Meat and butter from grass-fed animals contain a greater percentage of omega-3 fats than meat and butter from animals which were fattened on corn.
  • Flaxseed oil has a higher percentage of omega-3 fats than other seed oils.
  • High-oleic sunflower oil has the highest percentage of monounsaturated fat than other seed oils.
    • Other vegetable oils with high monounsaturated fat content include olive oil, avocado oil, and canola oil. [Note: Although olive oil is the source of monounsaturated fat that we hear about most, avocado oil is equally high in monounsaturated fat and has a higher smoke point, which makes it a better choice for high-heat cooking.]
  • Walnuts have a higher percentage of omega-3 fats than other nuts.
  • Macadamia nuts and almonds have the highest percentage of monounsaturated fats than other nuts, with cashews and peanuts not far behind. Nut butters, of course, reflect the fat composition of the nuts.

The point I am making is that while myths are simple, the truth is much more complex.

Take Home Lesson: Every vegetable oil and every seed oil has a unique composition of fats. Each has its unique benefits and unique drawbacks.

That is something you will want to think about the next time you read an article about the dangers or the benefits of all seed oils. Every seed oil is unique. No generalization applies to all of them.

Biochemistry 101 – Essential Fats

ProfessorLet’s start with the most important point.

  • Omega-6 fats and omega-3 fats are essential. Simply put, that means:
  • We can’t make them.
  • They are essential for life.
  • We must get them from our diet.

If they are essential, the next question is, “Why do we need them?” Let me start with a little “Biochemistry 101” and talk about their role in cell membranes and cellular regulation.

Cell Membranes:

  • You might think of cell membranes as a solid protective armor around the cells, but nothing could be farther from the truth. A better analogy would be the ocean that covers vast areas of our planet. Our membranes are quite fluid.
  • And that membrane fluidity is important. Our cell membranes contain receptors like the cholesterol receptor and insulin receptor that must cluster together for cholesterol and insulin to be transported into the cell. Those receptors cluster best when cell membranes are very fluid.
  • Our membranes are most fluid when they contain high levels of polyunsaturated fats (For membrane fluidity it doesn’t matter if they are omega-6 or omega-3). Conversely, our membranes are less fluid when they contain high levels of saturated fats.
  • And here is the most important point. Because our bodies cannot make omega-6 and omega-3 polyunsaturated fats, this is the one time it is literally true that, “We are what we eat”. If our diets are high in saturated fats, our membranes are high in saturated fats. If our diets are high in polyunsaturated fats, our membranes are high in polyunsaturated fats.
    • And the ratio of omega-6 and omega-3 polyunsaturated fats in our membranes reflects the ratio of omega-6 and omega-3 polyunsaturated fats in our diet.

Take Home Lesson: Diets high in omega-6 and/or omega-3 fats help lower cholesterol levels and improve blood sugar regulation.

Cellular Regulation:

  • Our cells also use the polyunsaturated fats in our cell membrane to make hormone-like substances called prostaglandins and leukotrienes that exert profound effects on nearby tissues. [Note: For the sake of simplicity, I will just talk about prostaglandins for the rest of this article, but what I say applies equally to leukotrienes.]
  • The enzymes that make prostaglandins do not distinguish between omega-6 and omega-3 polyunsaturated fats. They just use whatever polyunsaturated fat they come across.
  • That’s important because the effects of omega-6 and omega-3 prostaglandins are often different and are sometimes opposite.
  • Here’s where the “We are what we eat” principle comes into play. The ratio of omega-6 and omega-3s in our diet determines the omega-6 and omega-3 content of our membranes. And that determines the type of prostaglandins our cells produce.

Take Home Lessons:

  • Some of the benefits of omega-6s are unique because they are dependent on omega-6 prostaglandins. These benefits cannot be duplicated by diets high in omega-3s.
  • Because some effects of omega-6 and omega-3 prostaglandins are opposite, we need to look closely at the omega-6 to omega-3 ratio in the diet to optimize the health benefits of these two essential polyunsaturated fats.

Now, with Biochemistry 101 behind us, we are ready to look at the truth about omega-6 fats.

The Truth About Omega-6 Fats

Assortment Of Salad Dressing Bottles

Let’s start by looking at the pros and cons of omega-6 fats. 

Pros Of Omega-6 Fats:

Cellular Health: Omega-6 and fats are important for maintaining proper membrane fluidity. And omega-6 prostaglandins also regulate cell metabolism and cellular repair mechanisms.

Heart Health: Omega-6s are associated with lower risk of heart disease. This is caused by:

  • Lower cholesterol levels due to proper membrane fluidity which allows clustering of cholesterol receptors.
  • More flexible endothelial cells lining our arteries, which helps lower blood pressure and prevent blockage of the arteries by blood clots. This is most likely due to more fluid cell membranes and the production of beneficial prostaglandins.
  • Some of these benefits are duplicated by omega-3 fats, but the American Heart Association stated in a recent Health Advisory (WS Harris et al, Circulation, 119, 902-907, 2009) that omega-6 fats are essential for some heart health benefits. They cannot be replaced by omega-3s.

Brain Health: Omega-3s get most of the press here, but experts feel that omega-6s play an important and independent role as well.

Fetal Growth and Development: Omega-6 fats are essential for normal neural development and growth. The mechanism(s) for this benefit are ill-defined.

Other Benefits:

  • Omega-6 fats support healthy skin, hair, and bones. The mechanisms for these effects are unknown, but most experts feel they are independent of omega-3 fats.
  • Omega-6 fats are also important for reproductive health. Most experts think this is due to the production of omega-6 prostaglandins.

Take Home Lesson: Omega-6 fats are essential for a healthy heart, a healthy brain, and normal fetal growth and development.

Cons Of Omega-6 Fats:

Oxidation: Omega-6 (and omega-3) fats are very susceptible to oxidation, especially at high temperatures. This can lead to free radical formation, which can promote the formation of cancer cells.

You may have seen the statement that omega-6 fats cause cancer. This is an oversimplification. A more accurate statement would be, “Improperly used, any polyunsaturated fat may increase cancer risk. But this is largely avoidable. Here are the precautions I recommend:

  • Choose your source carefully.
  • For seeds and nuts look for freshness. If they look or taste funny, throw them out.
  • For oils choose reputable brands and choose ones that use low-heat processing. Also, look for ones with minimal processing. They may be cloudy rather than clear, but they will also contain naturally occurring antioxidants and polyphenols.
  • Don’t overheat them.
    • Most vegetable oils are only suitable for use as salad dressings and other room temperature cooking.
    • The exceptions are vegetable oils with high smoke points – for example, olive oil for stir fries and avocado oil for higher temperature cooking.
  • Store them safely. Don’t give them a chance to become oxidized.
    • We store sunflower seeds and almonds in our refrigerator and walnuts in our freezer.
    • We buy unsaturated vegetable oils in small quantities (so they are used up quickly) and store them in the refrigerator.

Take Home Lesson: Improperly used, omega-6 fats, like any unsaturated fat, can become oxidized and form free radicals (the kernel of truth). Choose your source carefully. Don’t overheat them. Store them safely.

FlamesInflammation: This is the one you hear the most about. You have been told that omega-6 vegetable oils (seed oils) cause inflammation. As a blanket statement, it is mostly untrue. But it does have a kernel of truth.

Let’s start with the kernel of truth:

  • Omega-6 fats are inflammatory only when compared to omega-3 fats. You have also been told that omega-6 fats are inflammatory when compared to saturated fats. This is false, as I will discuss below.

Let me elaborate on the first statement with a little more Biochemistry 101 (If you haven’t guessed, that’s my favorite topic. Once a professor, always a professor).

  • Omega-6 fats are converted into one inflammatory prostaglandin. Omega-3 fats are converted into several anti-inflammatory prostaglandins (This is an example of some omega-6 and omega-3 prostaglandins having opposite effects).
  • Because of their opposite effects on inflammation, some experts say that the optimal ratio of omega-6 to omega-3 fats is in the range of 1:1 to 4:1. But the typical American diet is around 15:1.

If the omega-6 to omega-3 ratio is important (and not every expert agrees that it is), the statement that we should avoid omega-6-containing vegetable oils (seed oils) because they are inflammatory is mostly untrue.

  • Every omega-6 oil has a different omega-6 to omega-3 ratio. For example,
    • Corn oil has a 50:1 ratio and sesame oil has a 42:1 ratio. If you are just going by omega-6 to omega-3 ratios, you might want to avoid these.
    • Soybean oil has a 7:1 ratio and extra virgin olive oil has a 5:1 ratio. They are almost in the optimal range.
    • Canola oil has a 2:1 ratio. It’s in the optimal range.
    • And flaxseed oil is the clear winner with a 1:4 ratio.

But the truth is also much more complex than you have been led to believe.

  • The kernel of truth is that omega-6 fats can be converted to an inflammatory prostaglandin.
  • But omega-6 fats can also be converted to anti-inflammatory prostaglandins. And some omega-6 fats such as GLA are anti-inflammatory.
  • Human clinical studies find that omega-6 fats either have no effect on inflammation or decrease it slightly (A Poli et al, International Journal of Molecular Sciences, 24, 4567, 2023).

Take Home Lesson: Omega-6 fats are converted into one inflammatory prostaglandin (the kernel of truth). But they are also converted to anti-inflammatory prostaglandins. The net effect in the human body is a slight anti-inflammatory effect.

The Truth About Saturated Fats

You have been told that saturated fats are anti-inflammatory and decrease the risk of heart disease. For many Americans those claims are enticing because it means they don’t have to change their diet. But are the claims true?

You have been told that these claims are based on science. There are clinical studies behind them. Is that true?

The problem is that there are a lot of bad studies on saturated fats in the literature, and the Dr. Strangeloves of the world cherry pick the ones that support their beliefs.

If you want to compare the effect of different kinds of fat on either inflammation or heart health, you must make sure that all other components of the diet are the same. Too many of these studies have compared a whole food diet high in saturated fat with the typical American diet high in omega-6 fats. The results are predictable. Anything is better than the typical American diet.

In a previous issue of “Health Tips From The Professor” I discussed the criteria for a good study of fats. High quality studies must:

  • Show the subjects stick with the new diet for the duration of the study. Subjects find it difficult to adhere to a diet to which they are not accustomed long term and often revert to their more familiar diet. This requires either very close monitoring of what the subjects are eating or measurement of fat membrane composition to verify diet adherence, or both.
  • Carefully control or measure what the saturated fats are replaced with. In good studies only the fat composition of the diet changes. All other components of the diet remain the same.
  • Last two years or more. The fats we eat determine the fat composition of our cell membranes, and that is what ultimately determines both inflammation in our bodies and our risk of dying from heart disease. While it is true to say, “We are what we eat”, changing the fat composition of our cell membranes does not occur overnight. It takes 2 years or more to achieve a 60-70% change in the fat composition of cell membranes.
  • Measures multiple markers of inflammation or actual cardiovascular end points such as heart attack, stroke, and deaths due to heart disease.

When studies are done that meet these criteria the results are as follows:

Inflammation (A Poli et al, International Journal of Molecular Sciences, 24: 4567, 2023):

  • Replacing saturated fats with omega-6 fats reduces inflammation by 8%.
  • Replacing saturated fats with omega-3 fats reduces inflammation by 48%

Heart Disease (FM Sacks et al, Circulation, 136, Number 3, 2017):

  • Replacing saturated fats with omega-6 from decreased the risk of heart disease by 24%.
  • Replacing saturated fats with a mixture of both omega-6 and omega-3 fats decreased the risk of heart disease by 29%. This is equivalent to statin therapy, without the side effects.
  • When the replacement of saturated fats with omega-6 and omega-3 fats occurred in the context of a heart healthy diet such as the Mediterranean diet, heart disease risk was reduced by 47%.

The Food and Nutrition Board of the Institute of Medicine recommends that Americans not exceed 10% of calories from saturated fat.

  • Two thirds of Americans exceed this limit.

The Food and Nutrition Board recommends that omega-6 fats be around 5-6% of calories. Because omega-6 fats play an important role in heart health, the American Heart Association recommends they be at 5-10% of calories.

  • Americans get around 6.5% of their calories from omega-6 fats.

Take Home Lesson: Replacing saturated fat with omega-6 fats reduces both inflammation and heart disease risk. Adding omega-3 fats reduces both even more. So, bringing omega-6 and omega-3 into a better balance is a good idea. But omega-6 fats are essential and are at the recommended intake for most Americans, so don’t do this by cutting back on healthy omega-6 fats. Instead, add some more omega-3s.

The Truth About Canola Oil

There are a lot of things to like about canola oil:

  • It is an excellent source of healthy omega-6 fats.
  • It has a good omega-6 to omega-3 ratio (2:1), which makes it anti-inflammatory.
  • It is also a good source of monounsaturated fats and has a moderate smoke point, which makes it suitable for low heat cooking.

So, why is it so unpopular? Unfortunately, it suffers from a lot of undeserved myths. Each has a kernel of truth. But like a secret passed around the room, the myths have grown with each repetition, and the truth has become unrecognizable.

So, let’s try to separate the myths from the truth.

Myth: It is genetically engineered.

Truth: It was created by old-fashioned plant breeding.


Myth: Canola oil contains toxic ingredients.

Truth:

  • Rapeseed oil comes from the oilseed rape plant (a relative of mustard).
  • Rapeseed oil contains erucic acid and glucosinolates, both of which can be toxic in large amounts (the kernel of truth).
  • Baldur Stefansson from the University of Manitoba bred a “double low” variety the oilseed rape plant which produces an oil that contains <2% of both erucic acid and glucosinolates and is safe for human consumption. This new oil was named canola oil (from Canada and ola for oil). This was achieved by conventional plant breeding. Not genetic engineering.
  • Both cultivars of the oilseed rape plant are still grown. Rapeseed oil is used for industrial purposes, and canola oil is used for human consumption.
  • Canola oil is tightly regulated in Canada, the US, and the EU to <2% erucic acid.
  • 98% of the canola oil sold in the US is grown in Canada and the northern US.

Myth: Canola oil is unhealthy.

Truth: Because it is one of the least expensive omega-6 oils, canola oil is often found as an ingredient in unhealthy, highly processed, food (the kernel of truth). The solution is simple. Avoid unhealthy foods. Adding a different kind of fat to unhealthy foods is not going to make them healthier.

The Truth About Seed Oils

By now I have covered most of the myths about seed oils in my sections on omega-6 fats, saturated fats, and canola oil, but here is a quick review.

Myth: All seed oils are…[add your favorite derogatory term here].

Truth: Every seed oil has a unique composition of fats. Each has its unique benefits and unique drawbacks.


Myth: Seed oils are genetically modified.

Truth: The plants producing canola oil and high oleic sunflower oil have been modified (the kernel of truth), but they were modified by conventional plant breeding rather than genetic engineering.


Myth: Seed oils contain toxic ingredients. This myth is most often directed at canola oil.

Truth: Rapeseed oil contains components that can be toxic at high levels (the kernel of truth). However, the rapeseed plant has been bred to produce canola oil with safe levels of those components.


Myth: Seed oils are inflammatory, which increases your risk of inflammatory diseases and heart disease.

Truth: Seed oils contain omega-6 fats which can be converted into one inflammatory prostaglandin (the kernel of truth). But they are also converted to anti-inflammatory prostaglandins. The net effect in well done human clinical trials is a slight anti-inflammatory effect.


Myth: Seed oils cause oxidative damage, which increases your risk of cancer.

Truth: Seed oils (like any polyunsaturated fat) are susceptible to oxidation, especially at high temperatures. This can lead to free radical formation and oxidative damage (the kernel of truth). But this is only true when you use them improperly. The solution is to chose your source wisely, store them safely, and to not overheat them when cooking.


Myth: Saturated fats are healthier than seed oils. Replacing saturated fat with the omega-6 fats found in seed oils increases inflammation and heart disease risk.

Truth: Many studies in this area of research are poorly designed. Well-designed studies show that replacing saturated fat with the omega-6 fats found in seed oils reduces both inflammation and heart disease risk.


Myth: Omega-3 fats are healthier than the omega-6 fats found in seed oils, so we should replace seed oils with omega-3 fats.

Fact: Omega-3 fats are more effective than omega-6 fats at reducing inflammation and heart disease risk (the kernel of truth). However, omega-6 fats are essential for a healthy heart, a healthy brain, and normal fetal growth and development. We can’t make them, so we must get them from our diet. Americans are currently consuming the recommended amount of omega-6 fats. So, we should not decrease the amount of omega-6 fats in our diet. Instead, we would benefit from adding more omega-3s to our diet.


Myth: Seed oils are highly processed. High heat processing alters the oils. Processing also removes beneficial antioxidants and polyphenols from the oils.

Truth: This is mostly true. The solution is to choose your brands carefully.

  • For oils choose reputable brands and choose ones that use low-heat processing. Also, look for ones with minimal processing. They may be cloudy rather than clear, but they will also contain naturally occurring antioxidants and polyphenols.
  • It’s not easy to choose your source carefully. But this difficulty is not unique to seed oils. For example:
    • The term EVO is supposed to mean extra virgin olive oil was used, but cheaper oils are sometimes blended into the olive oil to save money.
    • If a company wishes to use the term “grass fed” on their product, they must file a certification with the USDA, but the USDA does not inspect to determine whether the certification is accurate.
    • Seed oils are also found as an ingredient in unhealthy, highly processed foods. The solution here is simple. Avoid unhealthy foods. Adding a different kind of fat to unhealthy foods is not going to make them healthier.

For more details about each of these Truth statements, read the article above.

The Bottom Line

There are many myths about seed oils. Each myth has a kernel of truth but is mostly false. In this week’s “Health Tips From the Professor” I discuss the myths and truths about seed oils. Because this is a complex subject, I have broken it down into individual topics that address one or more seed oil myths before talking about seed oil myths directly.

The topics I covered are:

  • The truth about fats.
  • The truth about omega-6 fats.
  • The truth about saturated fats.
  • The truth about canola oil.
  • The truth about seed oils.

For more details read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure or prevent any disease.

_____________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

 _______________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.

Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”.

Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.



The News About Omega-3s Just Got Better

What Does This Study Mean For You? 

Author: Dr. Stephen Chaney 

good newsA recent meta-analysis (AA Bernasconi et al, Mayo Clinic Proceedings, 96: 1365-1375, 2021) of randomized clinical studies with over 150,000 patients showed that omega-3s reduced the risk of heart attacks by 13% and fatal heart attacks by 35%. Another major clinical study (T Chao et al, Nutrition, Metabolism and Cardiovascular Disease, 34: 537-547, 2024) with 30,000 patients found that omega-3s reduced all-cause mortality by 10%, cardiovascular mortality by 18%, heart attacks by 33%, and sudden cardiac death by 33%.

In short, the evidence that omega-3s reduce the risk of heart attacks and other forms of cardiovascular disease keeps getting stronger. However, the effect of omega-3s on heart failure is not as clear. Some studies suggest that omega-3s reduce the risk of heart failure and heart failure deaths. But other studies find little or no effect.

That’s unfortunate because heart failure is responsible for 45% of cardiovascular deaths and 14% of all deaths in the United States. In 2023 6.7 million Americans had heart failure, and that number is expected to increase to 8.5 million in 2030.

But numbers don’t tell the whole story. It is the trend in heart failure deaths that is truly concerning. Heart failure deaths per 100,000 Americans decreased by 20% between 1999 and 2012. Then the trend abruptly reversed. By 2021 heart failure deaths per 100,000 people was greater than in 1999. And the increase in heart failure deaths shows no signs of slowing down.

Nobody knows what is causing this rapid increase in heart failure deaths. But clearly the miracles of modern medicine are not working. And because the clinical studies on omega-3s and heart failure risk have been confusing, omega-3s are not currently recommended for heart failure patients.

This study (M A Jawad et al, Mayo Clinic Proceedings, 99: 1895-1904, 2024) was designed to clear up the confusion about omega-3s and heart failure risk.

How Was This Study Done?

clinical studyThis utilized data from the UK Biobank study. The UK Biobank study is an ongoing study that enrolled 502,366 subjects, aged 40-69, from the United Kingdom between April 1, 2007, and December 31, 2010. It regularly collects environmental, lifestyle, and genetic data on these individuals and tracks their health outcomes.

Within the study 273,033 participants had their blood levels of omega-3s determined by mass spectrometry. These measurements were used to calculate the Omega-3 Index (% of membrane fatty acids that are omega-3s) of these participants.

Of these participants:

  • 271,794 did not have a heart failure diagnosis at the time the omega-3 levels were determined. This group was used to evaluate the effect of omega-3s on the risk of developing heart failure.
  • 1,239 had a heart failure diagnosis at the time the omega-3 levels were determined. This group was used to determine whether omega-3s reduced the risk of death in heart failure patients.
  • 20,000 from this group had a repeat measurement of omega-3 levels around 4 years after the first measurement to determine the consistency of omega-3 levels. On average the repeat measurements were slightly lower, but the differences were small.

These participants were followed for an average of 13.7 years.

  • A diagnosis of heart failure was based on international diagnosis standards.
  • Deaths were identified by using the central death registry in the United Kingdom.

The News About Omega-3s Just Got Better

Omega-3s And Heart DiseaseThe data were clear. When participants with an Omega-3 Index in the top 20% were compared to those with an Omega-3 Index in the bottom 20%:

  • The risk of developing heart failure during the 13.7-year follow-up period was reduced by 21%.

When participants with a heart failure diagnosis prior to omega-3 measurement were compared in the same manner:

  • All-cause mortality was reduced by 48%
  • Cardiovascular mortality was reduced by 43%.

When the investigators looked at the effect of omega-3 supplementation in this population:

  • The risk of developing heart failure was 5% lower for those who reported omega-3 supplement use. I will discuss the reason for the discrepancy between comparisons based on omega-3 supplement use and comparisons based on blood levels of omega-3s below.

The authors concluded, “Higher plasma levels of marine omega-3 fatty acids were associated with a lower incidence of heart failure. Furthermore, among patients with preexisting heart failure, higher omega-3 levels were associated with lower risks of all-cause mortality and cardiovascular mortality. These findings suggest that increasing plasma omega-3 levels, whether by diet or supplementation, could reduce both risk for development of heart failure and death in those with prevalent heart failure.”

What Are The Strengths And Weaknesses Of This Study?

strengths and weaknessesThis was a very large, very well-done study. There is the usual caveat for this type of study, namely that it looks at associations and cannot prove cause and effect. However, it would be impossible to perform a double blind, placebo-controlled study with that many people for almost 14 years.

And heart failure does not happen overnight. Studies of the size and length are required to show meaningful effects of diet and/or supplementation on health outcomes like heart failure are not feasible.

Another major strength of this study is that it measured blood levels of omega-3s and showed those blood levels were relatively stable over time rather than relying on participants remembering what they ate and/or what supplements they used.

  • In terms of supplement use, studies like this one simply ask whether omega-3 supplements were used. They do not ask what the dose was, how frequently they were taken, the form of the omega-3 supplement (fish oil, EPA-only, DHA-only), and whether they were consumed with food or not (which affects absorption).
  • Studies that rely on diet recall and/or supplement use also have another weakness, namely individual differences in the absorption and utilization of omega-3 fatty acids. Simply put, two individuals getting the same dose of omega-3s from diet and supplementation may have different levels of omega-3s in their cellular membranes.
  • The authors felt it was these differences that explained why they saw a much stronger and more accurate effect of omega-3s on heart failure when they based their comparison on blood levels of omega-3s rather than omega-3 supplement use.

In short, this study significantly strengthens the evidence that omega-3s reduce the risk of heart failure and improve survival for those with heart failure.

What Does This Study Mean For You?

confusionHere are the take-home lessons from this study:

As I said above, this study significantly strengthens the evidence that omega-3s reduce the risk of heart failure and improve survival for those with heart failure. That means:

  • Optimizing your intake of omega-3s may be a good strategy for reducing your risk of heart failure. More importantly, optimizing omega-3 intake may also be a good strategy for improving your survival if you have been diagnosed with heart failure.
  • The authors said, “Because omega-3 is a well-tolerated over-the-counter nutrient…it is perplexing why this safe and affordable therapy…has not been widely incorporated into guideline-directed medical therapy for heart failure. Omega-3s…should be considered as add-on therapy to the standard regimen in the prevention and treatment of heart failure.” I agree.

But what is the optimum intake of omega-3s? This is what the authors had to say about that:

  • The top 20% of participants in this study had a blood Omega-3 Index of >5.45%, but this is not necessarily optimal.
  • Previous studies have suggested that an Omega-3 Index of 8% is the optimal target for reducing the risk of death from other forms of heart disease, and the authors feel this is also the optimal target for reducing the risk of heart failure.
  • The average American has an Omega-3 Index of 4-5%, which is associated with a high risk of heart disease.
  • Previous studies have indicated that an average intake of 1.4 g/day of EPA + DHA is required to move from an Omega-3 Index of 4% to 8%.

But the key word here is “average”.

  • None of us are average. We all absorb and retain omega-3s with different efficiencies. Many people will do great with 1.4 g/day. But some may need more to achieve an Omega-3 of 8%. And others will need less.
  • That’s why I recommend that you request blood tests of your Omega-3 Index and use those to guide you to an optimal 8% rather than relying on dosage of omega-3 supplements or frequency of omega-3-rich fish consumption alone.
  • However, I recognize that Omega-3 Index determinations are expensive and not all doctor’s offices are equipped to provide them. On average, an intake of 1-2 g/day of EPA + DHA is safe and likely effective at reducing risk of heart failure and other forms of heart disease. But it may not be optimal for you.

The Bottom Line 

Previous studies have shown that an optimal intake of omega-3s is likely to reduce the risk of heart attacks and deaths from heart disease. But the news about omega-3s just got better. A recent study strengthened the evidence that omega-3s also reduce the risk of heart failure and improve survival for those with heart failure.

The authors concluded, “Higher plasma levels of marine omega-3 fatty acids were associated with a lower incidence of heart failure. Furthermore, among patients with preexisting heart failure, higher omega-3 levels were associated with lower risks of all-cause mortality and cardiovascular mortality. These findings suggest that increasing plasma omega-3 levels, whether by diet or supplementation, could reduce both risk for development of heart failure and death in those with prevalent heart failure.”

For more details on this study and what it means for you, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

_______________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

________________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

 

Eating For A Healthy Heart

What Does This Mean For You?

Author: Dr. Stephen Chaney

You may remember the nursery rhyme, “Jack Sprat could eat no fat. His wife could eat no lean…” You may know people who fit these extremes. And in terms of diets these extremes might represent the vegan and keto diets in today’s world.

The nursery rhyme assures us that, “…between them they licked the platter clean.” But were their diets equally healthy? Which of them would have been more likely to live a long and healthy life?

And, since this is Heart Health Month, we might ask, “Which diet would have been better for their hearts?”

If you search Mr. Google – even with AI assist – you might be confused. That’s because AI bases its recommendations on the quantity of posts, not the accuracy of posts. And lots of media influencers recommend both diets, and just about every popular diet in between for heart health.

But what does good science say on the topic of heart healthy diets? Fortunately, a recent comprehensive review and meta-analysis (G. Riccardi et al, Cardiovascular Research, 118: 1118-1204, 2022) has answered that question.

How Was The Study Done?

clinical studyThe investigators reviewed 99 clinical studies with tens of thousands of participants that looked at the associations between foods or food groups and heart disease risk.

Most of the studies were “prospective cohort” studies in which:

  • Populations are divided into groups (cohorts) based on the foods they consume…
  • …and followed for a number of years (this is where the term “prospective” comes from)…
  • …and at the end of the study, the association between food and heart outcomes is measured.

However, the review also included several major randomized controlled clinical trials, including:

  • The DASH diet study.
  • The Lyon Diet Heart study.
  • The PREDIMED study.

Eating For A Healthy Heart

strong heartHere are the findings of the study. Most will sound very familiar. But you will note some subtle differences based on recent data.

The overall summary was that for a healthy adult population:

  • Low consumption of salt and foods of animal origin…
  • …and increased intake of plant foods…
  • …are associated with reduced heart disease risk.

Of course, we have known that for years. It’s when they broke the data down further that it became more interesting.

Foods Of Animal Origin:

  • Processed meats increase heart disease risk. A single serving of processed meat is associated with a 27% to 44% increased risk of heart disease. This is not new.
  • Unprocessed red meat is also associated with increased risk of heart disease, but this association is not as Steakconsistent as for processed meats. The authors noted that some of this may be due to differences in saturated fat content or cooking methods of the red meats included in individual studies.

But this analysis also showed that the effect of red meat on heart disease risk may be dose dependent. For example:

    • The studies they reviewed suggested that consuming ≥2 servings per day of red meat is associated with a 27% increased risk of heart disease. However, consuming <3 servings per week may not increase risk.
    • The idea that the effect of red meat on heart disease risk may be dose-dependent is novel. However, the authors said we also need to ask what replaces red meat in the diet. They postulated that when red meat consumption is decreased, it is often replaced with healthier protein sources.
  • White meat such as poultry does not appear to affect heart disease risk. This has been predicted by earlier reports, but this analysis strengthens those predictions.
  • Fish consumption decreases heart disease risk. This is not new. But this review added precision about recommended fish intake (2-4 servings/week) and a couple of caveats:
    • The heart benefits of fish may be due to their omega-3 content and may not apply equally to fish with lower omega-3 content.
    • The authors also expressed concerns about the sustainability of high-omega-3 fish populations. I would also add that our oceans are increasingly polluted, so contamination is another concern.
  • Egg consumption up to one egg/day does not appear to increase heart disease risk. This is consistent with the are eggs good for youcurrent American Heart Association recommendations.

However, the authors noted that the effect of eggs on serum cholesterol, and hence heart disease risk depends on several factors.

    • Genetics, obesity, and diabetes can make it more difficult to regulate serum cholesterol levels. For these individuals, eggs may need to be eaten only sparingly.
    • Diets low in saturated fat and high in fiber from plant foods help the body regulate serum cholesterol. Several studies suggest that eggs may decrease heart disease risk in the context of this type of diet.
  • Dairy: Neither low-fat nor high-fat dairy foods appear to influence heart disease risk. This is different from the standard recommendation to consume low-fat dairy foods. But it is in line with the trend of recent research studies on dairy and heart disease.

Once again, there were a couple of caveats:

    • There is increasing evidence that fermented dairy foods may decrease heart disease risk which may explain why certain high-fat cheeses and other high-fat fermented dairy foods appear to have a neutral or slightly beneficial effect on heart disease risk.
    • As with eggs the effect of high-fat dairy foods on heart disease risk may be influenced by genetics and diet context.

Foods Of Plant Origin: The effect of plant foods have been known for some time, and the most recent studies included in this analysis have not changed those conclusions.

  • Fruits and Vegetables consistently reduce heart disease risk in multiple studies. In each case, the optimal Vegan Foodsintake appears to be about 2 servings of each per day which provides an 18-21% risk reduction for vegetables and a 21-32% risk reduction for fruits.
  • Legumes (beans and peas) also consistently reduce heart disease risk in multiple studies. At the optimal intake of around 4 servings per week the risk reduction is around 14%.
  • Nuts also consistently reduce heart disease risk. At the optimal intake of around one serving (a handful) per day, the risk reduction is around 25%.
  • Cereals (grains) were divided into 3 categories:
    • Refined carbohydrates with a high glycemic index (e.g., white rice, white bread) are associated with increased heart disease risk in multiple studies probably due to their effect on blood sugar levels. And the increased risk is significant (Around 66% higher risk for every 2 servings).
    • Refined carbohydrates with a low glycemic index (e.g., pasta, corn tortillas) show an inconsistent effect on heart disease risk.
    • Whole grains are consistently associated with a lower heart disease risk. Two servings of whole grains per day are associated with a 25%-34% decreased risk.

Miscellaneous Foods:

  • Soft Drinks are associated with increased heart disease risk. One serving per day increases the risk by around 15-22% and recent evidence suggests that artificially sweetened soft drinks offer no heart health benefits compared to sugar sweetened soft drinks.
  • Coffee and Tea are both associated with decreased heart disease risk. For coffee the optimal benefit may occur at around 3 cups/day. Higher levels may have an adverse effect on heart disease risk.

Summary of Heart Health Recommendations

ScientistIf you are thinking that was a lot of information, the authors provided a numerical summary of their recommendations for a heart-healthy diet. They are:

  • Two servings per day of vegetables, fresh fruits, and whole grains.
  • One serving per day of nuts and seeds, low-glycemic index refined cereals, extra-virgin olive oil or non-tropical vegetable oils, and yogurt.
  • Four servings per week of legumes and fish.
  • No more than 3 servings per week of white meat, eggs, cheese, and milk.
  • No more than 2 servings per week of high-glycemic index refined starchy foods, red meat, and butter.
  • Only occasional consumption of processed meats.

What Does This Study Mean For You?

QuestionsOf course, nobody wants to follow a “diet by the numbers”. If you are like most of us, you want flexibility and you want to be able to eat some of your favorite foods. So, let me put these recommendations into a more “user friendly” form.

If you want a healthy heart:

  • Whole, unprocessed or minimally processed, plant foods are your friends.
  • Your heart-healthy foundation should be fruits, vegetables, whole grains, nuts and seeds, healthy plant oils, and legumes.
  • Your heart-healthy foundation can also include fermented dairy foods and low-glycemic index refined grains.
  • Your “go-to” beverages should be water, tea (both caffeinated and herbal teas), and coffee. You should avoid soft drinks and other sugar-sweetened or artificially sweetened beverages.
  • Once you have achieved a heart-healthy foundation you can add a few servings per week of white meat, eggs, cheese, and dairy, even high-fat dairy.
  • If you have good adherence to the heart-healthy foundation described above and no genetic or health issues that increase your risk of heart disease, you can probably eat more of these foods.
  • Conversely, if your adherence to the heart-healthy foundation is poor and/or you are at high risk of heart disease, you may wish to consume less of these foods.
  • If you have good adherence to the heart-healthy foundation, you can also add up to 1-2 servings of high-glycemic index refined carbohydrates, red meat, or butter per week. With red meat, you may want to consider it as a garnish that adds flavor to a plant-based meal rather than the centerpiece of the meal.
  • You should eat processed meats seldom or never.

The Bottom Line

A new comprehensive review and meta-analysis of 99 clinical studies with tens of thousands of participants has updated the correlation between foods and heart disease risk.

Many of the recommendations based on this analysis are identical to previous recommendations for a heart-healthy diet.

But there are some subtle changes to those recommendations based on the latest data.

For more details about this study and what a heart-healthy diet might look like for you, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

_______________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

_______________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

How Much Should You Walk?

Walking Your Way To Health 

Author: Dr. Stephen Chaney 

Overweight People ExercisingYou’ve made your New Year’s resolutions. And if you are like millions of Americans, you may already be making plans to join a gym, get a personal trainer, or join a spin class.

The problem is these are all expensive options. And a good portion of that money is wasted. To put it into perspective, let’s look at some statistics

  • Around 6 million Americans buy gym memberships every January.
    • 67% of those memberships are never used.
    • For those memberships used in January, another 50% are not in use 6 months later.
  • Americans spend about 1.6 billion dollars on unused gym memberships every year.
    • And that doesn’t include those gym memberships that are only occasionally used.

If you want to get fit and healthy in the new year, perhaps you should consider a less expensive option – like walking. Your only investments are a good pair of walking shoes and a device that keeps track of the number of steps you take (eg, Fitbit, smart watch, or smart phone).

You still may give up on your New Year’s goal of getting fitter at some point. But you won’t have wasted so much money.

Of course, you probably have some questions about the benefits of walking, such as:

1) Is walking enough to significantly improve my fitness and health?

2) How far (how many steps) should I walk?

3) How fast should I walk?

Fortunately, two recent studies (B del Pozo-Cruz et al, JAMA Internal Medicine, 182: 1139-1148, 2022) and (J del Pozo-Cruz et al, Diabetes Care, 45: 2156-2158, 2022) have answered all three questions.

How Were These Studies Done?

clinical studyThe first study (B del Pozo-Cruz et al, JAMA Internal Medicine, 182: 1139-1148, 2022) followed 78,500 participants (average age 61, 55% female, 97% white) enrolled in the UK Biobank study for an average of 7 years.

At the time of enrollment, each participant was given an accelerometer (a device that measures the number and frequency of steps) to wear on their dominant wrist for 24 hours/day for 7 days. The investigators used the accelerometer data to categorize several types of physical activity.

  • Daily step counts (the average number of steps per day for 7 days). These step counts were further subdivided into two categories:
    • Incidental steps (It was assumed that ˂40 steps/min represented steps taken that were incidental to normal daily activities).
    • Purposeful steps (It was assumed that ≥40 steps/min represented steps taken as part of planned exercise).
  • Stepping intensity (the highest frequency of steps/min averaged over 30 min intervals for all 7 days).

At the end of the study, each of these variables was correlated with the risk of premature deaths due to all causes, cancer, and heart disease.

The second study (J del Pozo-Cruz et al, Diabetes Care, 45: 2156-2158, 2022) was similar except that it:

  • Used data from 1687 adults (average age = 55, 56% male, with diabetes or prediabetes when the study began) in the 2005-2006 National Health and Nutrition Examination Survey in the US.
  • Followed participants for 9 years instead of 7.
  • Only measured total steps/day.
  • Correlated total steps per day with premature death for participants who already had prediabetes or diabetes when they entered the study.

Walking Your Way To Health

woman walking dogStudy 1 looked at the effect of walking on health outcomes in multiple ways.

#1: Increase in number of steps/day:

  • On average study participants took an average of 7200 steps per day, but this ranged from a low of 3,200 steps/day to a high of 12,200 steps/day.
  • Each increase of 2,000 steps/day was associated with a:
    • 8% decrease in all-cause mortality.
    • 11% decrease in cancer mortality.
    • 10% decrease in heart disease mortality.
  • Overall, increasing from 3,200 steps/day to 10,000 steps/day decreased all-cause, cancer, and heart disease mortality by around 36%.
  • There was no minimum threshold to this beneficial effect of walking on the risk of premature death.
  • The benefits of walking appeared to plateau at 10,000 steps/day.

#2: Increase in number of incidental steps/day (steps taken that are incidental to normal daily activities):

  • On average study participants took 3240 incidental steps/day, but this ranged from a low of 2,100 steps/day to a high of 4,400 steps/day.
  • Each 10% increase in incremental steps/day was associated with a:
    • 6% decrease in all-cause mortality.
    • 6% decrease in cancer mortality.
    • 10% decrease in heart disease mortality.

#3: Increase in number of purposeful steps/day (steps taken as part of planned exercise):

  • On average study participants took 4,600 purposeful steps/day, but this ranged from a low of 1,600 steps/day to a high of 8,600 steps/day.
  • Each 10% increase in purposeful steps/day was associated with a:
    • 7% decrease in all-cause mortality.
    • 8% decrease in cancer mortality.
    • 10% decrease in heart disease mortality.

#4: Increase in speed of walking or cadence. The measurement they used was “peak-30 cadence” – the Walking Fasthighest average steps/min during a 30-minute interval within a day:

  • On average study participants had a “peak-30 cadence” of 76 steps/min, but this ranged from a low of 47 steps/min to a high of 109 steps/min.
  • Each 10% increase in “peak-30 cadence” was associated with a:
    • 8% decrease in all-cause mortality.
    • 9% decrease in cancer mortality.
    • 14% decrease in heart disease mortality.
  • The benefits of walking rapidly (increase in “peak-30 cadence”) were in addition to the benefits seen by increasing the number of steps per day.
  • Overall, increasing from a “peak-30 cadence” of 47 steps/min to 109 steps/min decreased all-cause, cancer, and heart disease mortality by an additional 34%.
  • There was no minimum threshold to this beneficial effect of increasing “peak-30 cadence” (the speed of walking) on the risk of premature death.
  • The benefits of increasing “peak-30 cadence” appeared to plateau at 100 steps/min.

strong heart#5 Effect of walking on the prevention of heart disease and cancer: The investigators measured this by looking at the effect of walking on the “incidence” of heart disease and cancer (defined as new diagnoses of heart disease and cancer) during the study. They found.

  • Each 2,000-step increase in the total number of steps/day decreased the risk of developing heart disease and cancer by 4% during this 7-year study.
  • Each 10% increase in the number of purposeful steps/day decreased the risk of developing heart disease and cancer by 4% during this study.
  • Each 10% increase in “peak-30 cadence” decreased the risk of developing heart disease and cancer by 7% during this study.

The authors concluded, “The findings of this population-based…study of 78,500 individuals suggest that up to 10,000 steps/day may be associated with a lower risk of mortality and cancer and CVD incidence. Steps performed at a higher cadence may be associated with additional risk reduction, particularly for incident disease.”

Study 2 extended these findings to diabetes. They started with participants that had either prediabetes or diabetes diabetesand followed them for 9 years. They found that:

  • Study participants with prediabetes ranged from a low of 3,800 steps/day to a high of 10,700 steps/day.
    • Prediabetic participants walking 10,700 steps/day were 25% less likely to die during the study than participants walking only 3,800 steps/day.
  • Study participants with diabetes ranged from a low of 2,500 steps/day to a high of 10,200 steps/day.
    • Diabetic participants walking 10,200 steps/day were also 25% less likely to die during the study than participants walking only 2,500 steps/day.
  • Even small increases in the number of steps per day decreased the risk of premature death for both prediabetic and diabetic participants.
  • Once again, 10,000 steps/day appeared to be the optimal dose to lower the risk of premature death for both diabetic and prediabetic patients.

The authors of this study concluded, “Accumulating more steps/day up to ~10,000 steps/day may lower the risk of all-cause mortality of adults with prediabetes and diabetes.”

How Much Should You Walk?

Walking CoupleThat was a lot of information. You are probably wondering what it means for you. Let’s start with the big picture:

  • Going from couch potato to 10,000 steps per day may reduce your risk of premature death due to all causes, cancer, and heart disease by 36% (24% if you are already prediabetic or diabetic).
  • Increasing the speed with which you walk from 47 steps/min to 109 steps/min sustained for 30 minutes may reduce your risk of premature death by an additional 34%.

In other words, simply walking more and walking faster can have a significant effect on your health. I am not recommending walking as your only form of exercise. I’m just saying not to consider it inferior to other forms of exercise.

  • There is no lower limit to the benefits of walking. Even small increases in the number of steps/day you take and the speed with which you walk may have a beneficial effect on your health.

In other words, you don’t need to speed walk 10,000 steps/day to reap a benefit from walking. Even small increases are beneficial. That’s good news for those of you who may not be able to speed-walk long distances. It also means that if you are a couch potato, you don’t need to attempt 10,000 steps at high speed from day 1. You can work up to it gradually.

  • Incidental walking (walking that is incidental to your daily activities) is almost as beneficial as purposeful walking (walking as part of a planned exercise).

That’s good news for those of you who may not have time for long walks. It also means that advice like “park your car at the far end of the parking lot and walk” or “take the stairs rather than the elevator” can have a meaningful impact on your health.

  • The benefits of walking appear to max out at around 10,000 steps per day and a cadence of 100 steps/min sustained for 30 minutes.

That means once you get to those levels, it’s time to consider adding other kinds of exercise to your regimen. More and faster walking may offer little additional benefit.

Finally, in the words of the authors, “This information could be used to motivate the least active individuals to increase their steps and the more-active individuals to reach the 10,000-step target.”

The Bottom Line 

You’ve made your New Year’s resolutions. And if you are like millions of Americans, you may already be making plans to join a gym, get a personal trainer, or join a spin class.

If you want to get fit and healthy in the new year, perhaps you should also consider a less expensive option – like walking.

Of course, you probably have some questions about the benefits of walking, such as:

  1. Is walking enough to significantly improve my fitness and health?

2) How far (how many steps) should I walk?

3) How fast should I walk?

Fortunately, two recent studies have answered all three questions. They found:

  • Going from couch potato to 10,000 steps per day may reduce your risk of premature death due to all causes, cancer, and heart disease by 36% (24% if you are already prediabetic or diabetic).
  • Increasing the speed with which you walk from 47 steps/min to 109 steps/min sustained for 30 minutes may reduce your risk of premature death by an additional 34%.
  • There is no lower limit to the benefits of walking. Even small increases in the number of steps/day you take and the speed with which you walk may have a beneficial effect on your health.
  • Incidental walking (walking that is incidental to your daily activities) is almost as beneficial as purposeful walking (walking as part of a planned exercise).
  • The benefits of walking appear to max out at around 10,000 steps per day and a cadence of 100 steps/min sustained for 30 minutes.

In the words of the authors of these studies, “This information could be used to motivate the least active individuals to increase their steps and the more-active individuals to reach the 10,000-step target.”

For more details on these studies and what they mean for you, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

 _____________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

 ______________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.

Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”.

Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

Are Our Healthy Years Getting Shorter?

What Does This Mean For You?

Author: Dr. Stephen Chaney

If you’ve ever traveled the subway system in London, you can’t have missed the “Mind the Gap” signs warning not to put your foot in the gap between the subway and the platform.

That warning is more important than ever in an age where people look at their cell phones rather than where they are walking. Of course, if they are looking at their cell phones, they might miss the sign and…

But today’s “Health Tip” is not about subway gaps. It’s about a far more important gap – the gap between our healthspan (how many years we enjoy good health) and our lifespan (how many years we live).

A recent study (L Gimeno et al, The Journals of Gerontology, Series B, 79(8), gbae113, 2024) suggesting that our healthy years are getting shorter caught my attention.

All of us imagine that our golden years will be ones of vibrant health. We’ll travel to exotic places. We’ll take long walks in the mountains. We’ll play with our grandchildren. Life will be wonderful.

But if this study is correct, none of that will happen for many young Americans. They will be too frail and sick to enjoy their golden years. They will be surviving rather than thriving.

So, in today’s “Health Tips From the Professor” I will review the study and tell you what it means for you.

How Was The Study Done?

clinical studyThe investigators used data on 114,526 adults >50 (average age = 63) from developed countries (the United States, England, and continental Europe). Specifically, they used data from people who participated in the Healthy and Retirement Study (26,939 people in the United States), the English Longitudinal Study on Ageing (14,992 people in England), and the Survey of Health, Ageing, and Retirement (72,595 people in continental Europe) between 2004 and 2018.

These surveys collected data on health-related outcomes every 2 years. The outcomes measured were:

  • Six activities of daily living (ADLs) such as eating, bathing, and walking.
  • Four instrumental activities of daily living (IADLs) related to essential tasks such as grocery shopping or preparing a hot meal.
  • Seven measures of mobility difficulties and motor coordination tasks such as walking one block, lifting 10 pounds, or picking up a small coin from a flat surface.

The assumption was that the severity of limitations was ADL > IADL > mobility difficulties. This is based on previous research showing that a person with ADL limitations is likely to have IADL limitations and mobility difficulties. And a person with IADL limitations is likely to have mobility difficulties. Based on this assumption, they classified participants in this study into 4 disability categories:

  • Mild disability: ≥1 IADL limitations and any number of mobility difficulties.
  • Moderate disability: 1-2 ADL limitations with any number of IADL limitations and mobility difficulties.
  • Severe disability: ≥3 ADL limitations with any number of IADL limitations and mobility difficulties.

The study also measured the prevalence (percent of the population) with:

  • Obesity
  • Heart disease.
  • Diabetes
  • Cancer
  • Lung disease.
  • High blood pressure.
  • High cholesterol.

Finally, the study also measured grip strength because loss of grip strength is considered an indicator of future disabilities.

The unique feature of this study is it compared the health and disability of people who were at the same age when tested but were born in different decades ranging from 1925 to 1955.

Because of the rapid change in diet and lifestyle following World War II, the health and disability of people born in the 1936-1945 decade encompassing World War II was used as the standard to which all other decades were compared.

Are Our Healthy Years Getting Shorter?

Some of you may have skipped over the previous section, so I will repeat the way these data were analyzed because it is crucial to your understanding of the study.

“The unique feature of this study is it compared the health and disability of people who were at the same age when tested but were born in different decades ranging from 1925 to 1955.

Because of the rapid change in diet and lifestyle following World War II, the health and disability of people born in the 1936-1945 decade encompassing World War II was used as the standard to which all other decades were compared.”

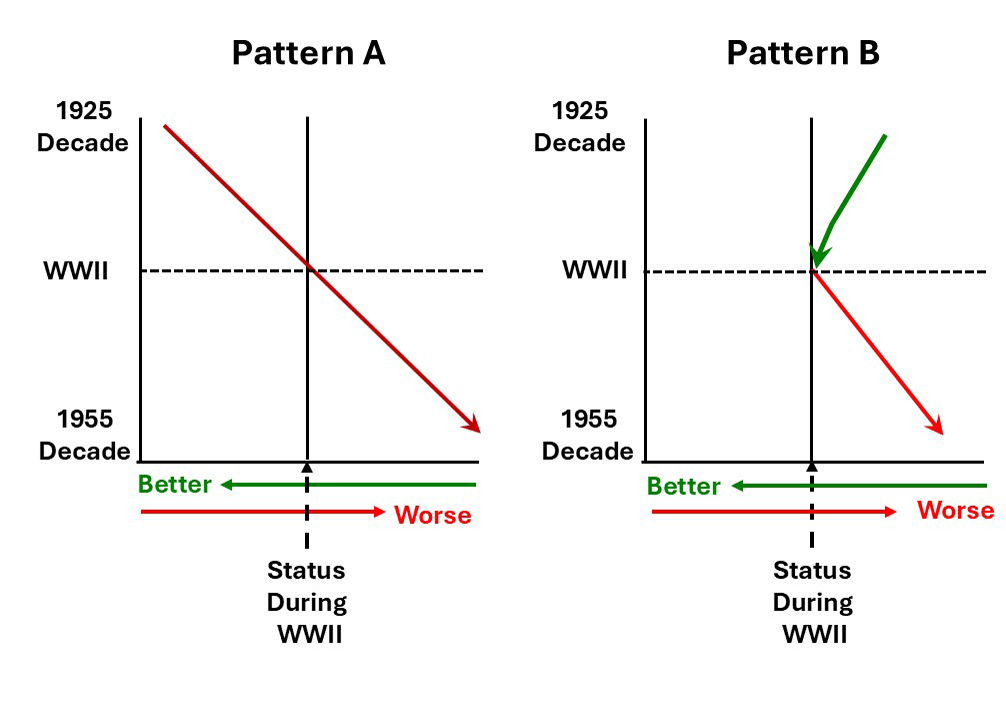
When looking at data from the United States, there were two distinct patterns.

The vertical line in the center of the graph represents the health and disability status of people born during World War II because all comparisons in this study were to people born in the decade encompassing World War II. A worsening of health and disabilities is indicated in red and an improvement in health and disabilities is shown in green. 

Pattern A was characteristic of a constant worsening of health and disabilities from people born in the decade starting in 1925 to people born in the decade starting in 1955.

This pattern was seen for:

  • Obesity
  • Heart disease.
  • Diabetes
  • Lung disease.
  • High blood pressure.
  • High cholesterol.
  • Severe disabilities.
  • Reduction in grip strength.

Remember, this study is measuring health and disability of people at the same age. The only difference is when they were born. It tells us people in their 50s, 60s, or 70s born in 1955 or later are in poorer health than people of the same age who were born in 1925.

And it’s not just the United States. For obesity and health parameters the pattern was the same for England and Europe. For severe disabilities the pattern was the same for England but was not as clear for Europe.

Two things should be noted for this pattern:

  • The worsening of health and the increase in severe disabilities comes despite the vast improvements in the health care systems in these countries and improved understanding of the causes of these diseases.
  • Obesity is likely a major driver of our declining health and increased disability. However, it is not the only driver. If the investigators had graphed the percentage of highly processed foods in the diet or the decline in regular exercise, the pattern would have been similar.

Pattern B shows an improvement in the period leading up to World War II and a deterioration in the period after World War II. The authors interpreted the improvement prior to World War II as due to improvements in health care and the deterioration after World War II as due to changes in diet and lifestyle.

This is the pattern seen for mild and moderate disabilities in the United States. The pattern for mild and moderate disabilities was not as clear for England and Europe.

The authors concluded, “In all regions, we found evidence for worsening health across cohorts [groups of people born in successive decades], particularly for those born after 1945.”

What Does This Study Mean For You?

QuestionsI don’t want to overinterpret this study. This study breaks new ground, but it has some limitations that I would characterize with three statements:

  • It is a very difficult study to do perfectly.
  • There are several factors that could affect the interpretation of the data and the outcome of the study.
  • The authors made a valiant effort to correct for any factors that could have affected the outcome.

For more details about the factors that might affect the outcome of the study and how the authors corrected for them, read the study.

However, this is the first study to use this approach to gauge the decrease in healthy years (healthspan) in developed countries over the past 40 years. It has its flaws, but it is consistent with several other studies documenting declining health in the current generation of young adults. For example, in a recent issue of “Health Tips From the Professor” I reviewed a study showing that colon cancer rates are increasing at an alarming rate for young adults in this country.

At the beginning of this article, I talked about the gap between our healthspan (how many years we enjoy good health) and our lifespan (how many years we live).

This study suggests that the onset of significant health issues and disabilities is occurring at a younger age today than for people born before World War II. In short, it suggests that our healthspan (the number of healthy years) is getting shorter.

This study did not look at lifespan, but numerous studies show that our lifespan is still increasing. So, the gap between healthspan and lifespan appears to be getting larger. In simple terms this means that when today’s young adults reach their “golden years”, they may spend more of those years in poor health than those of us born in the 1940’s.

But, what does this mean for you? The take home lesson should be, “This doesn’t have to be. You don’t have to be frail and sickly in your golden years. We know how to prevent this.”

  • It starts with a healthy diet – a whole food, primarily plant-based diet with lots of colorful fruits and vegetables, whole grains, nuts and seeds.
  • Add in a regular exercise program with a mixture of aerobic and resistance exercises.
  • Include an individualized supplement program.

You notice I didn’t list weight control as one of the top three prevention strategies. That’s because I don’t recommend fad diets and rapid weight loss programs. If you do the first three things well, your weight will come off naturally – a little bit at a time.

And once you have mastered all four things, you will increase your healthy years and narrow the gap between your healthspan and your lifespan. You can look forward to golden years filled with vitality and adventure.

The Bottom Line

A recent study used an innovative approach to quantify the deterioration in health and the physical ability to function well in daily activities as we age. The unique feature of this study is it compared the health and disability of people who were at the same age when tested but were born in different decades ranging from 1925 to 1955.

The study found a constant worsening of health and disabilities from people born in the decade starting in 1925 to people born in the decade starting in 1955 for:

  • Obesity
  • Heart disease.
  • Diabetes
  • Lung disease.
  • High blood pressure.
  • High cholesterol.
  • Severe disabilities.

The authors concluded, “We found evidence for worsening health across cohorts [groups of people born in successive decades], particularly for those born since 1945.”

In short, people born in recent years have fewer healthy years (a shorter healthspan) than people born before World War II. And since our lifespans are getting longer, this means the gap between our healthspan and our lifespan is increasing.

All of us imagine that our golden years will be ones of vibrant health. We’ll travel to exotic places. We’ll take long walks in the mountains. We’ll play with our grandchildren. Life will be wonderful.

But if this study is correct, none of that will happen for many of today’s young adults. They will be too frail and sick to enjoy their golden years.

For more details about this study and how you can increase your healthy years, narrow the gap between your healthspan and your lifespan, and look forward to golden years filled with vitality and adventure, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

 ______________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

_______________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

Is Olive Oil Overrated?

What Is The Truth About Olive Oil And You? 

Author: Dr. Stephen Chaney 

You may have seen headlines claiming that olive oil doesn’t deserve its “health halo”. It isn’t as healthy as many experts have claimed. It is overrated.

These headlines aren’t referring to the scandalous practice of selling “extra virgin” olive oil that contains cheaper oils. That is another topic for another day.

The headlines are claiming that, while the Mediterranean diet is healthy, it is fruits, vegetables, whole grains, legumes, and fish that make the Mediterranean diet healthy. Their claim is that olive oil has little to do with it.

To evaluate these claims I have reviewed the study (AK Krenek et al, Journal of the American Heart Association, Volume 13, Number 15:e035034, July 24, 2024) behind the headlines.

And to provide context, I have also reviewed another recent study (M Guasch-Ferre et al, Journal of the American College of Cardiology, Volume 79, Number 2, 2022).

How Were These Studies Done?

clinical studyThe two studies were very different:

The First Study used a randomized cross-over design to compare high and low olive oil diets.

In the randomized cross-over design participants were randomly assigned to one of the two diets at the beginning of the study. They followed that diet plan for 4 weeks. And after a one week “washout” they followed the other diet plan for 4 weeks. In this type of study each participant serves as their own control.

Study participants (50 obese participants, average age = 64, 75% women, 72% white, ≥ 5% risk of heart disease) were all eating a typical American diet.

Each of the experimental diets was a whole food plant-based diet, with comparable amounts of fruits, vegetables, whole grains, legumes, nuts, and seeds. Both diets were high in fiber, low in added sugar, and contained less than an ounce of animal products a day. In other words, the base diet was a healthy plant-based diet.

Participants in the high olive oil group were asked to add 4 tablespoons/day of extra virgin olive oil to their diet while participants in the low olive oil group were asked to restrict their olive oil intake to < 1 teaspoon/day.

No effort was made to control portion sizes or caloric intake. As we will see below, this was a major weakness of the study. As you might expect, fat intake was significantly greater for those on the high olive oil diet (49% of calories) compared to the low olive oil diet (32% of calories). Consequently, caloric intake was also significantly greater on the high olive oil diet.

All participants met with a dietitian/chef at the beginning of the study and were given access to online training programs and a dietitian hotline for questions. Dietary intake was measured by a 24-hour dietary recall 4-7 times prior to the study and 4 times during each diet period.

Fasting blood and urine samples were collected prior to the study and at the end of each 4-week diet period to measure biomarkers with possible predictive value for heart disease, such as LDL cholesterol.

The Second Study was a prospective cohort study using data obtained from 60,582 women in the Nurses Health Study and 31,801 men in the Health Professionals Follow-Up Study.

In a prospective cohort study a cohort or group of people (in this case, the 60,582 women and 31,801 men in the two studies) are followed over time (in this case for 28 years from1990 to 2018). The study then measures the association between some aspect of their diet and lifestyle (in this case the kind of fat in their diet) and health outcomes at the end of the study (in this case all-cause mortality, cardiovascular mortality, cancer mortality, neurodegenerative disease mortality, and respiratory disease mortality).

A strength of this study was that the diet of all participants was assessed every 4 years, which allowed the investigators to track changes in their diet over time. The intake of most fats was remarkably stable over the entire 28-year duration of the study.

However, as the bad news about margarine and the good news about olive oil entered the popular media, margarine consumption declined, and olive oil consumption increased. Because the investigators were able to track these changes over time, they were able to correct for them in their data analysis.

Is Olive Oil Overrated?

thumbs down symbolResults From The First Study: If we restrict ourselves to statistically significant observations, the results were as follows:

  • Switching from the baseline diet (typical American diet) to either the high olive oil or low olive oil diets for 4 weeks resulted in a significant decrease in total cholesterol, LDL cholesterol, HDL cholesterol, and blood glucose levels.
  • In this case, there was no statistically significant difference between the two diets.

However, when transitioning from the low olive oil diet to the high olive oil diet and from the high olive oil diet to the low olive oil diet, some statistically significant differences were observed.

For example, transitioning from the high olive oil diet to the low olive oil diet resulted in:

  • A 7% decrease in total cholesterol.
  • An 11% decrease in LDL-cholesterol.
  • A 2.2% decrease in HDL-cholesterol.
  • A 2% decrease in blood glucose levels.

And transitioning from the low olive oil diet to the high olive oil diet resulted in:

  • A 14% increase in total cholesterol.
  • A 14% increase in LDL-cholesterol.
  • A 15% increase in HDL-cholesterol.
  • A 17% decrease in blood glucose levels.

The authors of this study said, “Although both [whole food, primarily plant-based] diets improved [risk factors for heart disease], a low olive oil intervention may provide superior LDL-cholesterol lowering in individuals at highest risk [of heart disease]. Future studies are needed to determine if these short-term effects are sustainable and translate to improvements in cardiac outcomes…Nevertheless, a whole food primarily plant-based diet with relatively lower olive oil may be a useful tool for clinicians for improving cardiovascular risk compared with greater olive oil intake.”

The authors also went on to say, “…olive oil may not be the beneficial additive of a Mediterranean diet.”

thumbs upResults From The Second Study:

Higher intake of olive oil (>0.5 tablespoons/day compared to ≤1 teaspoon/day) resulted in:

  • A 19% decrease in the risk of all-cause mortality. And when that was broken down by cause it amounted to:
    • A 19% decrease in the risk of cardiovascular mortality.
    • A 17% decrease in the risk of cancer mortality.
    • A 29% decrease in the risk of neurodegenerative disease mortality.
    • An 18% decrease in the risk of respiratory disease mortality.

In a substitution analysis calculating the effect of consuming 10 g/day of olive oil instead of 10 g/day of:

  • Butter resulted in a 14% decrease in the risk of all-cause mortality.
  • Margarine or dairy fat resulted in a 13% decrease in the risk of all-cause mortality.
  • Mayonnaise resulted in a 9% decrease in the risk of all-cause mortality.
  • Other vegetable oils had no effect on all-cause mortality.
  • Results were similar when the investigators looked at the effect of replacing fats with olive oil on mortality due to cardiovascular disease, cancer, neurodegenerative disease, and respiratory disease.

The authors of the second study concluded, “Higher olive oil intake was associated with lower risk of total and cause-specific mortality. Replacing margarine, butter, mayonnaise, and dairy fat with olive oil was associated with lower risk of mortality.”

How can we reconcile these conflicting viewpoints? Let me start by looking at the flaws in the first study. Then I will summarize the “truth” about olive oil based on what these two studies tell us.

Is The Study Behind The Headlines Misleading?

flawsFirst let me summarize why I consider the study to be misleading. Then I will discuss why the headlines about the study are misleading.

Why The Study Is Misleading: The main conclusion of this study was that adding olive oil to a primarily plant-based diet increased the risk of heart disease. While this study is well-designed in some respects, it is flawed in others. I will summarize the flaws here:

Flaw Number 1: The authors rely on the relative effects of the high and low olive oil diets on LDL-cholesterol levels in predicting the effect of the two diets on heart disease risk. However, there is a major problem with this argument:

  • HDL-cholesterol levels move in the same direction. Both are decreased in the transition from the high olive oil to the low olive oil diet. Both are increased in the transition from the low olive oil to high olive oil diet. The ratio of HDL to LDL cholesterol changes very little, so it is almost impossible to predict what effect these changes will have on heart disease outcomes.

Flaw Number 2: This is related to the flaw I mentioned earlier. No effort was made to control portion size or caloric intake of participants on these diets. The high olive oil diet added 4 tablespoons of olive oil to the low olive oil diet. This significantly increased the fat and caloric intake of participants on the high olive oil diet.

  • Participants lost weight on both diets, but weight loss was significantly greater on the low olive oil diet. In their discussion, the authors admitted that the greater reduction in LDL-cholesterol on the low olive oil diet could have been due to the greater reduction in weight on that diet.

Flaw Number 3: I call this the “straw man” flaw. By adding 4 tablespoons of olive oil to the high olive oil diet the authors created the equivalent of a straw man that was easy knock over. Even if their conclusions were correct, nobody has recommended the addition of 4 tablespoons of olive oil to any diet as a heart-healthy approach.

Mediterraneans don’t add 4 tablespoons of olive oil to their diet. Olive oil is part of the foods they eat and the way they prepare their food.

Why The Headlines Are Misleading: Of course, the headlines were misleading because they ignored the many flaws of the study.

However, I find it amusing that some of the headlines came from “Forks Over Knives” an organization that advocates for a very low-fat plant-based diet. They were using this study to question the value of olive oil as part of a whole-food plant-based diet.

However, when you look at the study, 32% of calories came from fat in the low olive oil diet, and 49% of calories came from fat in the high olive oil diet.

For perspective:

  • The low-fat whole-food plant-based diet recommended by “Forks Over Knives” has <10-15% of calories from fat.
  • The Mediterranean diet typically contains 35-40% of calories from fat.
    • Around 18-19% of that is monounsaturated fat.
    • Around 8% of that is saturated fat.
  • The typical American diet also contains 35-40% of calories from fat.
    • Around 12-14% of that is monounsaturated fat.
    • Around 12% of that is saturated fat.

In other words, the low olive oil diet in this study resembles the fat content of the Mediterranean and typical American diets, not the low-fat whole food plant-based diet recommended by “Forks Over Knives”.

And the high olive oil diet contains fat levels not seen in any natural diet. Except for a few keto enthusiasts, I don’t know of any experts who think getting almost 50% of your calories from any kind of fat is a good thing.

What Is The Truth About Olive Oil And You?

The TruthAs described above, the study behind the headlines is a very small, very short study with multiple flaws. So, you can ignore headlines like “Olive oil is overrated” or “Olive oil doesn’t deserve its health halo.”

The second study I discussed is much larger (92,383 participants) and of much longer duration (28 years). More importantly, it measures health outcomes, not blood biomarkers that might predict health outcomes.

Finally, the second study was not measuring the health benefits of the Mediterranean diet, as many other studies have done. It was looking at the effect of varying olive oil intakes in the American diet. The high olive oil intakes in this study were less than those seen in the Mediterranean diet. This is good news for the average American who may feel overwhelmed trying to adopt to a Mediterranean diet.

This study reinforces previous studies showing that olive oil is healthy. But let me put this into context.

  • Olive oil is not a superfood. This study showed that it is no healthier than other plant oils. It is, however, considered one of the best vegetable oils for sauteing. It is also less susceptible to oxidation than seed oils, although I still recommend you store it in the refrigerator.
  • It is not something you add to your diet. It is something you incorporate into your diet. People who live in Mediterranean regions:
    • Cook with olive oil.
    • Use olive oil in their salad dressings and drizzle a little olive oil on cooked vegetable and pasta dishes instead of adding butter.
    • Dip their bread in olive oil rather than using butter or mayonnaise.
    • Use it in spreads like tapenade or hummus.
    • Use olives in cooking.
  • Finally, look for extra virgin olive oil. That doesn’t mean you need to spend “an arm and a leg”. But I would do a little online research before I bought the cheapest brand at the discount store.

The Bottom Line

You may have seen recent headlines claiming that olive oil is overrated and that it doesn’t deserve its “health halo”. So, I looked at the study behind the headlines.

It was a very small, very short study with multiple flaws. You can forget the headlines.

For context I also reviewed another recent study. It was a much larger (92,383 participants) and longer duration (28 years) study. More importantly, it measured actual health outcomes, not just blood biomarkers that might predict health outcomes.

It concluded that olive oil is good for us. It is healthier than most fats commonly found in the American diet, but it is no healthier than other plant oils.

For more details on these studies, what they mean for you, and how to incorporate more olive oil into your diet read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure or prevent any disease.

______________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

_____________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.

Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”.

Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.


For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

Are All Plant-Based Diets Healthy?

Why Are Plant-Based Diets Healthy?

Author: Dr. Stephen Chaney

Unless you are like Rip van Winkle and have been asleep for the past 30 years, you have probably heard that plant-based diets are good for you. In fact, that advice is sound. It is based on multiple long-term studies.

But you may still be hesitant to make the switch. You are probably wondering if you have to be a vegan purist to benefit from a plant-based diet. If so, you are wondering whether you can make that drastic a change in your diet. Or, you may have already decided “that is a bridge too far” and don’t want to even consider it.

So, one important question is, “Do you have to go vegan to benefit from a plant-based diet?”

On the other hand, “Big Food, Inc” has made it easier than ever to switch to more “plant-based” eating. After all, sugar comes from plants. And highly processed grains come from plants. Add a few chemicals and you can come up with an endless supply of highly processed plant-based foods.

So, another important question is, “Can a diet of highly processed plant-based foods be as healthy as a diet of whole, unprocessed plant-foods?”

The study (Y. Wang et al., Nutrition Journal, 22: 46, 2023) I am reviewing today was designed to answer these two questions. It also represents the first meta-analysis to combine data from studies on the effects of plant-based diets on diabetes, heart disease, cancer, and mortality into a single study.

How Was The Study Done?

clinical studyThe investigators performed a meta-analysis of 76 studies with 2,230,443 participants that looked at the associations of plant-based dietary patterns and the incidence of type 2 diabetes, cardiovascular disease, cancer, and mortality among adults 18 years or older.

The characteristics of study participants ranged from:

  • 25 to 87 years old.
  • BMI of 20 to 30.

And the duration of the studies within the meta-analysis ranged from 2 to 36 years.

The adherence to plant-based diets was defined as higher consumption of plant-based foods and lower consumption or exclusion of animal-based foods.

The meta-analysis also included studies looking at the effect of changing from a more animal-based to a more plant-based dietary pattern.

The meta-analysis included studies looking at the benefit of vegan and vegetarian diets. In terms of participants these studies represented just over 50% of the data in the meta-analysis. So, this meta-analysis was ideally positioned to determine whether vegan and vegetarian diets were more beneficial than other primarily plant-based dietary patterns that included some animal foods.

The methodology used to classify diets as primarily plant-based varied from study to study. But in each case the study participants were divided into quartiles ranging from consuming the most plant-based diet to consuming the least plant-based diet.

The study then compared study participants with the highest adherence to plant-based diets to those with the lowest adherence to plant-based diets with respect to type 2 diabetes, cardiovascular disease, cancer, and mortality.

Finally, the study also compared adherence to healthy plant-based dietary patterns (whole or minimally processed fruits, vegetables, whole grains, beans, nuts, and seeds) to unhealthy plant-based dietary patterns (foods and drinks with added sugar, highly processed plant foods, and starchy vegetables).

Are Plant-Based Diets Healthy?

When comparing highest to lowest adherence to plant-based dietary patterns the risk of:

  • Type-2 diabetes was reduced by 18%.
  • Cardiovascular disease was reduced by 10%.
  • Cancer was reduced by 12%.
  • Mortality was reduced by 16%.

In short, all the news was good for primarily plant-based dietary patterns.

Are All Plant-Based Diets Healthy?

Increased adherence to a healthy plant-based dietary pattern (That term is defined in the methods section above) was associated with an even better reduction in disease risk. For example:

  • Type-2 diabetes was reduced by 21%.
  • Cardiovascular disease was reduced by 15%.
  • Cancer was reduced by 13%.
  • Mortality was reduced by 14%, which was statistically indistinguishable from the reduction in mortality associated with all plant-based dietary patterns above.

Factory FarmIn contrast, increased adherence to an unhealthy plant-based dietary pattern was associated with increased risks of disease. For example:

  • The risk of type 2 diabetes increased by 8%.
  • The risk of cardiovascular disease increased by 14%.
  • The risk of cancer increased by 7%.
  • The risk of mortality increased by 16%.

In short, plant-based dietary patterns consisting of whole or minimally processed plant foods are good for you. Plant-based dietary patterns consisting of highly processed plant foods are not.

Are Vegan and Vegetarian Diets More Beneficial Than Other Plant-Based Dietary Patterns?

Mediterranean Diet FoodsTwenty seven of the studies within this meta-analysis compared vegetarian or vegan dietary patterns with animal-based dietary patterns. These studies had 1,343,967 participants, which amounts to 57% of the participants in the meta-analysis.

Thus, this meta-analysis was well positioned to determine relative benefits of vegan and vegetarian diets compared to other primarily plant-based dietary patterns that include some animal foods. The investigators reported that:

  • The risk reduction for type 2 diabetes was greater in studies with vegan and vegetarian diets than in studies with other primarily plant-based diets.
  • No other statistically significant benefits were observed for vegan and vegetarian diets compared to other primarily plant-based diets.

In short, you don’t need to become a vegan to experience the health benefits of a plant-based diet.

In contrast, increased adherence to an unhealthy plant-based dietary pattern was associated with increased risks of disease. For example:

  • The risk of type 2 diabetes increased by 8%.
  • The risk of cardiovascular disease increased by 14%.
  • The risk of cancer increased by 7%.
  • The risk of mortality increased by 16%.

In short, plant-based dietary patterns consisting of whole or minimally processed plant foods are good for you. Plant-based dietary patterns consisting of highly processed plant foods are not.

What If You Change From An Animal-Based To A Plant-Based Diet?

Food ChoicesIf you have been consuming an animal-based diet for years, you may be wondering whether it is too late to change. Has the damage already been done?

Six studies within this meta-analysis examined the effect of changing from an animal-based diet to a plant-based diet on type 2 diabetes and mortality. Changing to a more plant-based dietary pattern:

  • Reduced diabetes by 17% and mortality by 5%.

In short, it’s never too late to switch to a more plant-based dietary pattern.

Why Are Plant-Based Diets Healthy?

The short answer is that we don’t know for sure, but the authors mentioned several popular hypotheses.

  • Obesity is a risk factor for type 2 diabetes, cardiovascular disease, and certain types of cancer. And studies have shown that people consuming plant-based diets tend to weigh less.
  • The increased fiber content and higher ratio of polyunsaturated fats to saturated fats lower cholesterol levels and improve blood lipid profiles, which are associated with a lower risk of cardiovascular disease.
  • Plant-based diets are anti-inflammatory, which reduces the risk of all three diseases.
  • Plant foods are rich in polyphenols and other phytonutrients that are associated with reduced risk of cardiovascular disease, lower blood pressure, and improvements in insulin sensitivity.
  • Plant foods are metabolized by gut bacteria to metabolites that are associated with reduced risk of type 2 diabetes and cardiovascular disease.
  • Plant foods support healthy gut bacteria associated with a reduced risk of several diseases.
  • Finally, plant-based dietary patterns are associated with no or reduced consumption of red and processed meats, which increase the risk of type 2 diabetes, cardiovascular disease, and certain types of cancer.

For a more detailed discussion read the article).

What Does This Study Mean For You?

The authors of this study concluded, “Higher adherence to plant-based dietary patterns, especially from healthy sources, may be universally beneficial for the primary prevention of type 2 diabetes, cardiovascular disease, cancer, and mortality. The current study provides further evidence in support of current recommendations that emphasize consuming high-quality plant-based foods for achieving optimal health.”

“Future studies are needed to elucidate…mechanistic pathways linking plant-based diets with multiple disease outcomes.”

I would just like to emphasize a few points:

  • These are all association studies. It takes decades for diseases like diabetes, heart disease, and cancer to develop. So, it is impossible to confirm these findings with double blind, placebo-controlled studies. However, when you have 76 studies with over 2 million participants all pointing to the same conclusion, it is hard to ignore the findings.
  • The good news is that you don’t have to become a vegan to experience these benefits. There are many healthy primarily plant-based diets available. Choose the one that best fits your food preferences and lifestyle.
  • Be aware that whatever diet you choose, Big Food Inc is only too happy to provide you with highly processed foods that fit that dietary pattern. Don’t fall for that trap. Stick with whole or minimally processed plant foods.
  • If your current diet isn’t the best, it is never too late to switch to a healthier primarily plant-based diet.

The Bottom Line

A recent meta-analysis of 76 studies with 2,230,443 participants looked at the associations of plant-based dietary patterns and the incidence of type 2 diabetes, cardiovascular disease, cancer, and mortality among adults 18 years or older.

The authors of the study concluded, “Higher adherence to plant-based dietary patterns, especially from healthy sources, may be universally beneficial for the primary prevention of type 2 diabetes, cardiovascular disease, cancer, and mortality. The current study provides further evidence in support of current recommendations that emphasize consuminh high-quality plant-based foods for achieving optimal health.”

Other key points from the study are:

  • These are all association studies. It takes decades for diseases like diabetes, heart disease, and cancer to develop. So, it is impossible to confirm these findings with double blind, placebo-controlled studies. However, when you have 76 studies with over 2 million participants all pointing to the same conclusion, it is hard to ignore the findings.
  • The good news is that you don’t have to become a vegan to experience these benefits. There are many healthy primarily plant-based diets available. Choose the one that best fits your food preferences and lifestyle.
  • Be aware that whatever diet you choose, Big Food Inc is only too happy to provide you with highly processed foods that fit that dietary pattern. Don’t fall for that trap. Stick with whole or minimally processed plant foods.
  • If your current diet isn’t the best, it is never too late to switch to a healthier primarily plant-based diet.

For more details about how the authors came to these conclusions and what they mean for you, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

_______________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

 ______________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

Are Calcium Supplements Safe?

What Does This Study Mean For You?

Author: Dr. Stephen Chaney 

Pendulum
Pendulum

Should you avoid calcium supplements because they increase your risk of heart disease? Some headlines and blog posts would have you believe that. You may have been told that by your doctor. But is it true?

Unfortunately, this is another example of the swinging pendulum that we often see in supplement studies. One day a study comes out saying that calcium supplements increase the risk of heart disease. A few months later another study comes out saying that is not true. Calcium supplements don’t increase heart disease risk.

The pendulum keeps swinging until you are totally confused. You don’t know what to believe. And “experts” (including your doctor) pick one side or the other depending on what they believe about supplements in general.

I have told you before that good scientists wait until multiple studies have been done and base their opinion based on what the preponderance of studies show. I can tell you that multiple studies have been done and the preponderance of studies show that calcium supplements do not increase the risk of heart disease. But that doesn’t prove that calcium supplements are safe. It just shows they are likely to be safe.

That is why the authors of the current study (X Huo et al, Current Developments In Nutrition, volume 7, Issue 3: 100046, March 2023) analyzed the weaknesses of previous studies and tried to design a study that lacked those weaknesses.

How Was This Study Done?

clinical studyThe investigators searched through the literature to identify all placebo-controlled, randomized clinical trials (the gold standard for clinical studies) assessing the effects of calcium supplements alone or calcium supplements with vitamin D on heart disease, stroke, and all-cause mortality.

They restricted their analysis to studies with at least 500 participants that lasted for at least a year. They further restricted their analysis to studies whose authors were willing to share unpublished data on the number of participants in each treatment group who had a heart attack, stroke, or any other kind of heart disease; died from heart disease; or died from all causes during the study.

They ended up with 11 clinical studies in their analysis. The breakdown was as follows:

  • Seven studies with 8,634 participants compared calcium alone with placebo.
    • Participants in these studies averaged 71 years old and were 79% female.
    • The daily calcium dose varied from 1.0 to 1.5 g/day.
    • The mean duration of treatment was 4.1 years (range = 2-5 years).
  • Six studies with 46,804 participants compared calcium plus vitamin D with placebo.
    • Participants in these studies averaged 65 years old and were 98% female.
    • The daily calcium dose varied from 1.0 to 1.5 g/day and the daily vitamin D dose ranged from 400 to 2,000 IU/d.
    • The mean duration of treatment was 6 years (range = 1.5-7 years).
  • In case you were wondering about the math, some studies included both calcium alone versus placebo and calcium plus vitamin D versus placebo.

The authors then combined the data from all 11 studies and performed a meta-analysis on the effect of calcium alone on adverse heart outcomes and calcium plus vitamin D on adverse heart outcomes.

Are Calcium Supplements Safe? 

calcium supplementsThe results were clear-cut.

  • Calcium alone was not significantly associated with any increased risk of heart attack, stroke, heart disease of any kind, deaths from heart disease, and deaths from all causes.
  • Calcium with vitamin D was not significantly associated with any excess risk of heart attack, stroke, heart disease, deaths from heart disease, and deaths from all causes.

In their discussion, the authors pointed out two caveats to their conclusions:

  • In the calcium only portion of the meta-analysis the number of participants who experienced a stroke or types of heart disease other than heart attack and stroke was very small. So, they could not exclude an absolute increased risk of 0.3-0.5% per year for these types of rare events.
  • The participants in the 11 studies included in their meta-analysis were not selected based on their risk of heart disease. So, the authors could not exclude the possibility that calcium supplements might increase the risk of heart disease in people who were already at high risk of heart disease.

The authors concluded, “This meta-analysis demonstrated that calcium supplements were not associated with any significant hazard for heart disease, stroke, or all-cause mortality…Hence, for people with low bone density and low absolute risks of heart disease, the present report demonstrates no concern about excess heart disease risks associated with calcium supplements.

However, further large trials are needed to assess the efficacy and safety of combined supplementation with calcium and vitamin D for the prevention of osteoporotic fracture in older people at high risk of heart disease.”

What Does This Study Mean For You?

Questioning WomanAs I said above, the preponderance of evidence suggests that calcium supplementation does not increase your risk of heart disease. This study reinforces that conclusion.

I can’t guarantee that some future study won’t come to the opposite conclusion, and the pendulum will swing again. And I can’t guarantee that your doctor has kept up with the most recent literature on calcium supplementation and heart disease risk.

The authors of this study also pointed out that we don’t have any clinical studies on the effect of calcium on heart disease risk if you are already at high risk of heart disease. So, if you are at high risk of heart disease, any advice that I or your doctor give you about calcium supplementation might be wrong. We simply don’t know.

Finally, I realize that you may be equally confused about whether calcium supplementation can strengthen your bones and reduce your risk of osteoporosis. I won’t discuss that question today. Instead, I will refer you to two previous articles I have written in “Health Tips From the Professor” on that topic.

The first article discusses the flaws in previous studies claiming that calcium supplements are ineffective at increasing bone density and preventing osteoporotic fracture.

The second article describes a bone-healthy lifestyle.

The Bottom Line

While the preponderance of studies have shown that calcium supplementation does not increase the risk of heart disease, that conclusion remains controversial.

To clarify that issue, a group of investigators searched through the literature to identify all placebo-controlled, randomized clinical trials (the gold standard for clinical studies) assessing the effects of calcium supplements alone or calcium supplements with vitamin D on heart disease, stroke, and all-cause mortality. They then performed a meta-analysis of those clinical studies.

Their meta-analysis showed that:

  • Calcium alone was not significantly associated with any increased risk of heart attack, stroke, heart disease of any kind, deaths from heart disease, and deaths from all causes.
  • Calcium with vitamin D was not significantly associated with any excess risk of heart attack, stroke, heart disease, deaths from heart disease, and deaths from all causes.

This study strengthens the conclusion that calcium supplementation does not increase the risk of heart disease.

For more details about the study and references discussing the effect of calcium supplementation on bone density, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

______________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

_______________________________________________________________________

About The Author

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

Are Omega-3 Supplements Safe?

The Flaws And Blind Spots In This Study

Author: Dr. Stephen Chaney

Pendulum
Pendulum

Has the omega-3 pendulum swung again? The recent headlines are downright scary. For example:

  • “Fish Oil May Increase the Risk of Stroke and Heart Conditions.”
  • “Fish Oil Supplements May Cause Harm, Study Finds. Is It Time to Ditch Them?”
  • “Fish Oil Supplements May Lead to Heart Problems”.
  • “Regular Use of Fish Oil Supplements Might Increase, Rather Than Lessen, The Risk of First Time Heart Disease and Stroke Among Those in Good Cardiovascular Health.”

Yikes! That sounds bad. Should we be thinking about giving up our omega-3 supplements?

But wait. Just a few weeks earlier we were reading headlines about the benefits and lack of side effects from omega-3 supplements. That’s confusing. Which headlines are correct?

To answer these questions:

  • I will point out the flaws and blind spots in the study.
  • I will strip away the hyperbole and put the headlines into perspective.

How Was The Study Done?

clinical studyThe investigators made use of data from the UK Biobank Study. The UK Biobank Study is a large, long-term study in the United Kingdom which was designed to investigate the contributions of genetic predisposition and environmental exposure [including diet and supplementation] to the development of disease.

The UK Biobank Study enrolled 502,461 participants, aged 40-69 years, between January 1st, 2006 and December 31st, 2010. Participants were followed from entry into the program until March 31st 2021, an average of 11.9 years.

The current study excluded any participants who had a diagnosis of atrial fibrillation, heart failure, heart attack, stroke, or cancer at entry into the study, leaving 415,737 participants.

The participants were:

  • 55% women.
  • Average age of 56 years, with 83.4% of them below 65 years old at entry into the study.
  • 94.5% white.

The study was designed in a unique manner, in that it was designed to test the effect of omega-3 supplements on 6 specific transitions:

  • Primary prevention. This measured the transition of healthy (no diagnosed heart disease) people to either atrial fibrillation, major cardiovascular events, or death.
  • Secondary prevention. This measured the transition from atrial fibrillation to either major cardiovascular events or death.
  • Tertiary prevention. This measured the transition from major cardiovascular events to death.
  • Major cardiovascular events were further broken down to heart attacks, stroke and heart failure.

Participants were asked whether they used fish oil supplements when they entered the study and were categorized as either regular users or non-users. [Note: The users were not asked the dose or brand of fish oil supplements they used.]

Deaths were obtained from the national death registry and disease diagnosis from the National Health Service.

Are Omega-3 Supplements Safe?

omega-3 fish oil supplementHere is what the study found.

Primary Prevention – For healthy individuals (defined as having no diagnosed heart disease) using omega-3 supplements for an average of 11.9 years:

  • Increased the risk of atrial fibrillation by 13%.
  • Did not affect the risk of major cardiovascular events and death were unaffected by omega-3 supplementation.
  • When major cardiovascular events were broken down to their component parts, omega-3 supplementation:
    • Decreased the risk of heart failure by 8%.
    • Increased the risk of stroke by 5% (this was just barely statistically significance).
    • Did not affect the risk of heart attack.

Secondary Prevention – For individuals with atrial fibrillation omega-3 supplementation:

  • Decreased the risk of major cardiovascular events by 9%.
  • Decreased the risk of death by 8%.
  • When major cardiovascular events were broken down into their component parts, omega-3 supplementation:
  • Decreased the risk of heart attacks by 15%.
  • Had no effect on the risk of stroke or heart failure.

Tertiary Prevention – For people who suffered major cardiovascular events during the study omega-3 thumbs upsupplementation:

  • Decreased the risk of death by 8%.

Since this is a very complex set of data, I have coded positive results in green and negative results in red.

And as if these complexities were not enough, when the investigators broke these effects down by population groups:

  • Omega-3 supplementation decreased the transition from healthy to death for men (7% decrease) and participants older than 65 (9% decrease).

I will discuss the significance of these observations below.

The authors concluded, “Regular use of fish oil supplements might be a risk factor for atrial fibrillation and stroke among the general population but could be beneficial for [reducing] progression of cardiovascular disease from atrial fibrillation to major adverse cardiovascular events, and from atrial fibrillation to death.”

In short, they were suggesting that omega-3 supplements should be avoided by the general population because they have no positive benefits and might increase the risk of atrial fibrillation and stroke. But omega-3 supplements may be useful for those who already have heart disease.

Some of the articles you may have read about the study repeated this message. Others just emphasized the negative aspects of the study.

But is this message accurate? Let me start by discussing the flaws, blind spots, and hidden data in this study. Then I will summarize the 3 key findings of the study and tell you what they mean for you.

The Flaws, Blind Spots, And Hidden Data In This Study

flawsFlaws: As I said above, there were two major flaws in the study.

Flaw #1: The study did not identify the dose of supplement used. This is important because the increased risk of atrial fibrillation and stroke is primarily seen in clinical trials using high dose omega-3 supplements.

Flaw #2: This was an association study which cannot prove cause and effect. However, the authors of this study reported it as showing that omega-3 supplement use caused atrial fibrillation and stroke – and all the news reports on the study have repeated that claim.

Flaw #3: Other experts have pointed out that the authors inflated the risks associated with omega-3 supplementation by reporting relative risk rather than absolute risk. Let me try to simplify the distinction.

The risk of atrial fibrillation was 4.24% in the non-supplement users and 4.80% in the omega-3 supplement users. That is an absolute increase in risk of 0.56% (4.80% – 4.24%). This is the increase in risk you actually experience. In contrast, 4.80% is 13% greater than 4.24%, which is how relative risk is calculated.

In response to the questions you are probably thinking:

  • Yes, this is a perfect example of the Mark Twain quote, “There are lies. There are damn lies. And then there are statistics.”
  • Yes, all the percentages reported in this study are based on relative risk and are, therefore, inflated. However, I do not have access to their data, so I cannot tell you the absolute risk associated with their other observations.

Blind Spots: In their paper the investigators recommended against the use of omega-3 supplements to prevent heart disease because their data showed:

  • No benefit of omega-3 supplementation for preventing major cardiovascular events and deaths in a healthy population.
  • But did suggest an increased risk of atrial fibrillation and stroke in that same population.

However, their blind spot was in underestimating the difficulty of showing the benefit of any intervention in a healthy population. The example I always use is statin drugs. Statin Drugs:

  • Dramatically reduce the risk of a second heart attack and/or death in people who have already had a heart attack.
  • Reduce the risk of heart attacks in people who are at high risk of heart attacks.
  • Cannot be shown to reduce the risk of heart attacks in a healthy population.

This study suggests that omega-3 supplements are no different. In this study, omega-3 supplements:

  • Reduced the risk of death in people who had already experienced a major cardiovascular event like a heart attack or stroke.
  • Reduced the risk of major cardiovascular events and death in people with atrial fibrillation, which puts them at high risk for a heart attack or stroke.
  • Could not be shown to reduce the risk of major cardiovascular events or deaths in a healthy population.

Hidden Data: There are some important data that were buried in the text and supplemental figures but were Skepticignored in the concluding remarks of this study and all the articles written about it. For example:

  • The original study and all articles written about the study reported that omega-3 supplementation increased the risk of stroke in otherwise healthy individuals but ignored the observation that omega-3 supplementation decreased the risk of heart failure in that same group.

The second example of hidden data likely represents another blind spot of the authors. They concluded that omega-3 supplementation had no benefit for healthy individuals without asking whether omega-3 supplements might benefit higher-risk subpopulations within this group. To help you understand this statement let me start by giving you some perspective.

As I said above, statin drugs cannot be shown to reduce the risk of heart attacks in a healthy population. But when you include people at high risk of heart disease with healthy people in the dataset, you start to see a reduced risk of heart attacks.

Similarly, with supplements you often see no benefits with the general population, which is what is usually reported in the media. But when you look at higher risk groups within that population, the benefits of supplementation emerge.

This study is no different:

  • For healthy individuals, omega-3 supplementation had no effect on deaths during the 12-year follow-up period.
  • However, omega-3 supplementation reduced the risk of death by 9% for both men and people ≥ 65. These represent two groups with elevated risk of heart disease within the otherwise healthy population.
  • Once again, these data were completely ignored.

What Does This Study Mean For You?

This study made 3 major points:

Point #1: Let me start with the one you’ve heard the most about. The risk of atrial fibrillation and stroke associated with omega-3 supplementation is real. We should not ignore it.

But what this study and most of the reports on the study didn’t tell you is that the risk is dose dependent. The risk is primarily seen with high doses of omega-3s. While no one has done a comprehensive dose response analysis, I can tell you that these side effects are:

  • Seldom reported in clinical studies at doses of 1 gm/day or less.
  • Sometimes reported in clinical studies at doses of ≥2 gm/day.
  • Frequently reported in clinical studies at doses of ≥4 gm/day.

However, atrial fibrillation and stroke occur in a very small percentage of omega-3 users, even at 4 gm/day. At this point we have no idea why some people are susceptible to these side effects and others are not. More research in this area is clearly needed.

Until we know more about who is at risk, my recommendation for people who are trying to reduce the risk of heart disease is to rely on something called the Omega-3 Index to determine your individual omega-3 needs rather than using high-dose omega-3 supplements.

  • The Omega-3 Index measures the amount of omega-3 fatty acids in your tissues. It is determined by the amount of omega-3s you consume and how you metabolize them, so it is individualized to you.
  • An Omega-3 Index of 4% is associated with a high risk of heart disease, while an Omega-3 Index of 8% is associated with a low risk of heart disease. There is no evidence that more than 8% provides additional benefit.
  • Most importantly, it only takes 1-1.6 gm/day of omega-3s to raise your Omega-3 Index from 4% to 8%. At these doses your risk of atrial fibrillation and stroke is extremely small.

For example, a recent meta-analysis of 29 studies with a total of 183,292 participants reported that people with an 8% Omega-3 Index had:

  • Decreased risk of ischemic stroke (stroke due to blood clots) with no detectable increased risk of hemorrhagic stroke (stroke due to bleeding), and…
  • No detectable increased risk of atrial fibrillation.

I recommend getting your Omega-3 Index determined, and if it is low, increasing your omega-3 intake to get it into the 8% range. Some people go from 4% to 8% more rapidly than others, so you may need to repeat the test several times to optimize your Omega-3 Index.

If your health professional doesn’t have access to the Omega-3 Index test, you can order it from https://omegaquant.com (I have no financial stake in this company, but I know it as a reputable source of the Omega-3 Index test).

Does The Professor Plan To Reduce His Intake Of Omega-3 Fatty Acids? Three weeks ago, I shared thatprofessor owl my wife and I have been taking around 3 gm/day of omega-3 supplements for the past 40 years. Now that the association of atrial fibrillation and stroke with high dose omega-3 intake has been firmly established, some of you may be wondering whether we plan to decrease our intake of omega-3 supplements.

The answer is, “No”. Remember that the increased risk of atrial fibrillation and stroke is only seen for a small subset of people taking high-dose omega-3 supplements. If we were part of that subset, we would likely have experienced one of those side effects by now.

However, if you are considering omega-3 supplementation for the first time, you don’t know whether you are part of that subset or not. So, my advice remains the same. Rely on optimizing your Omega-3 Index rather than high-dose omega-3 supplementation.

Point #2: Healthy individuals (those with no symptoms of heart disease) do not benefit from omega-3 supplementation. As I pointed out above, this ignores data from their study, namely.

  • Omega-3 supplementation reduced the risk of heart failure in healthy subjects.
  • Omega-3 supplementation reduced the risk of death in higher risk groups within the healthy population (namely men and people 65 and older).

Confusion Clinical StudiesAs I discussed above, this is a pattern seen with statin drugs and most nutritional supplements. Simply put, you can’t show any benefit of statin drugs or most nutritional supplements in a “healthy” population, but you can show benefit when you focus on higher risk individuals within the “healthy” population.

The problem, of course, is that most of us don’t really know whether we are “healthy” or not. For millions of Americans the first indication that they are at risk from heart disease is sudden death from a heart attack or stroke.

With that in mind, I will leave the decision about whether you want to supplement with omega-3s up to you. But if you decide to supplement, I recommend you optimize your Omega-3 Index rather than using a high dose omega-3 supplement.

Point #3: People with heart disease benefit from omega-3 supplementation. This recommendation is becoming non-controversial, so I won’t comment further other than to say high dose omega-3 supplements are probably not needed unless prescribed by your health professional.

The Bottom Line

You have been asking me about recent headlines saying that omega-3 supplements may increase rather than decrease the risk of heart disease. So, I analyzed the study behind the headlines. The study makes 3 claims:

  • Omega-3 supplements increase the risk of atrial fibrillation and stroke when taken by healthy people.
  • Omega-3 supplements are of no benefit for healthy individuals.
  • Omega-3 supplements are beneficial for people who have heart disease.

In the article above I review the flaws, blind spots, and hidden data in the article and discuss what it means for you.

For more details about this study and what it means for you read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure, or prevent any disease.

 ______________________________________________________________________________

My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

 _______________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.  Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”. Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

Is The Mediterranean Diet Healthy For Women?

What Does This Study Mean For You? 

Author: Dr. Stephen Chaney 

There is a well-known health disparity in clinical studies related to health. For years most of the studies have been done by men for men. Women have been assumed to experience the same benefits and risks from diet choices as men. But that hasn’t always proven to be true.

The Mediterranean diet is no exception. For example, it has garnered a reputation of reducing heart disease risk for both men and women.

However, most studies on the Mediterranean diet have included primarily male participants or did not report sex specific differences in outcomes.

And the few studies that reported sex specific outcomes have been inconsistent.

  • Some studies have found that men and women benefitted equally from the Mediterranean diet.
  • Other studies have reported that men benefitted more than women.

However, these were all small studies. No meta-analyses have been reported that focused on the heart benefits of the Mediterranean diet for women.

The study (A Pant et al., Heart; 109: 1208-1215, 2023) I will describe today was designed to fill that gap.

How Was The Study Done?

clinical studyThe investigators started by screening the literature to find studies that:

  • Measured adherence to the Mediterranean diet using the original MDS (Mediterranean Diet Score) or more recent modifications of the MDS.
  • Included women ≥18 years without previous diagnosis of clinical or subclinical heart disease.
  • Performed the study with only women participants or organized their data so that the data pertaining to women could be extracted from the study.

The investigators then performed a meta-analysis on data from 722,495 women in 16 studies published between 2006 and 2021 that met these criteria. These studies followed the women for an average of 12.5 years. The studies were primarily conducted in the United States and Europe.

The individual studies divided participants into either quintiles or quartiles and compared participants with the highest adherence to the Mediterranean diet to those with the lowest adherence.

  • The primary outcomes measured were total mortality and the incidence of CVD, cardiovascular disease (defined as including CHD (coronary heart disease), myocardial infarction (heart attack), stroke, heart failure, and cardiovascular death).
  • The secondary outcomes measured were stroke and CHD, coronary heart disease (heart disease caused by atherosclerotic plaque build up in the coronary arteries).

Is The Mediterranean Diet Healthy For Women?

Mediterranean Diet FoodsWhen comparing the highest to the lowest adherence to the Mediterranean diet:

  • The incidence of CVD (cardiovascular disease) was reduced by 24%.
  • Total mortality during the ~12.5-year follow-up was reduced by 23%.
  • The incidence of CHD (coronary heart disease) was reduced by 25%.
  • The risk of stroke was reduced by 13%, but that risk reduction was not statistically significant.
    • The risk reduction for both CVD and total mortality was similar to that previously reported for men.
    • Risk reduction for CVD was slightly higher for women of European descent (24%) than for women of non-European descent (21%). The later category included women of Asian, Native-Hawaiian, and African – American descent.

The authors concluded, “This study supports a beneficial effect of the Mediterranean diet on the primary prevention of CVD and death in women and is an important step in enabling sex-specific guidelines.”

I would add that the data from women of non-European decent suggests that genetic background and/or ethnicity may influence the effectiveness of the Mediterranean diet at reducing heart disease risk, but this effect appears to be small.

What Does This Mean For You?

The results of this study are not unexpected. But that doesn’t mean that studies with women are not valuable. There have been several examples in recent years where health or medical advice based on studies with men needed to be modified for females once the studies were repeated with women.

Before covering what this study means for you, I should point out that while women often fear breast cancer most, heart disease is their number one killer, as the graph on the left shows. In fact, a woman’s risk of dying from coronary heart disease is 6 times greater than her risk of dying from breast cancer.

This study shows that following a Mediterranean–style diet lowers their risk of developing and dying from heart disease. But the Mediterranean diet is not alone in providing these health benefits. It is simply a whole food, primarily plant-based diet that reflects the food preferences of the Mediterranean region.

The DASH diet, which reflects the food preferences of Americans, and the Nordic diet, which reflects the food preferences of the Scandinavian countries, are equally heart healthy. In fact, any whole food, primarily plant-based diet will reduce the risk of heart disease. You should choose the one that best fits your food preferences and lifestyle.

Of course, diet is just part of a holistic approach for reducing heart disease risk. Other important risk reduction strategies include:

  • Don’t smoke.
  • Exercise and maintain a healthy weight.
  • Manage stress.
  • Avoid or limit alcohol.
  • Know your numbers (cholesterol, triglycerides, and blood pressure, for example).
  • Manage other health conditions that increase the risk of heart disease (high blood pressure, diabetes, and high cholesterol, for example).

The Bottom Line

Most studies on the heart health benefits of the Mediterranean diet have been done with men or have not analyzed the data from men and women separately. A recent meta-analysis combining data from 16 studies with 722,495 women showed that the Mediterranean diet was just as heart healthy for women as it was for men.

The authors concluded, “This study supports a beneficial effect of the Mediterranean diet on the primary prevention of CVD and death in women and is an important step in enabling sex-specific guidelines.”

For more details on this study and information on other diets that are heart healthy, read the article above.

These statements have not been evaluated by the Food and Drug Administration. This information is not intended to diagnose, treat, cure or prevent any disease.

_____________________________________________________________________________My My posts and “Health Tips From the Professor” articles carefully avoid claims about any brand of supplement or manufacturer of supplements. However, I am often asked by representatives of supplement companies if they can share them with their customers.

My answer is, “Yes, as long as you share only the article without any additions or alterations. In particular, you should avoid adding any mention of your company or your company’s products. If you were to do that, you could be making what the FTC and FDA consider a “misleading health claim” that could result in legal action against you and the company you represent.

For more detail about FTC regulations for health claims, see this link.

https://www.ftc.gov/business-guidance/resources/health-products-compliance-guidance

 _____________________________________________________________________

About The Author 

Dr. Chaney has a BS in Chemistry from Duke University and a PhD in Biochemistry from UCLA. He is Professor Emeritus from the University of North Carolina where he taught biochemistry and nutrition to medical and dental students for 40 years.

Dr. Chaney won numerous teaching awards at UNC, including the Academy of Educators “Excellence in Teaching Lifetime Achievement Award”.

Dr Chaney also ran an active cancer research program at UNC and published over 100 scientific articles and reviews in peer-reviewed scientific journals. In addition, he authored two chapters on nutrition in one of the leading biochemistry text books for medical students.

Since retiring from the University of North Carolina, he has been writing a weekly health blog called “Health Tips From the Professor”. He has also written two best-selling books, “Slaying the Food Myths” and “Slaying the Supplement Myths”. And most recently he has created an online lifestyle change course, “Create Your Personal Health Zone”. For more information visit https://chaneyhealth.com.

For the past 45 years Dr. Chaney and his wife Suzanne have been helping people improve their health holistically through a combination of good diet, exercise, weight control and appropriate supplementation.

Health Tips From The Professor